Since another question from a doc is related to TB, I'll post that here as well:
55 y old gentleman presented with few weeks history of progressive dyspne and right sided pleuritic chest pain, with history of contact with a case of pulmonary TB, no symptoms of toxemia, clinically the patient got signs of right sided pleural effusion which was aspirated and shown to be lymphocytic exudate,because the patient also presented with hoaseness of voice CT chest was done showed no lung masses or lymphadenopathy, BAL showed no malignant cells, PPD test was highly positive, laryngeal examination showed cordal polyp. culturing the fluid and sputum for TB was negativethe patient was started on antituberculous ttt , 1st 2 months quadrible therpy and then dual therapy and the patient still have re accumulating effusion? any suggestions?
Showing posts with label Tuberculosis. Show all posts
Showing posts with label Tuberculosis. Show all posts
Friday, November 30, 2007


TB treatment and a followup BAL
A physcian from Florida recently asked how one should approach the following. A younger man from a TB-endemic area with cavitary upper lobe lesions. He is not productive of sputum. Obviously, the physician elected to treat empirically for TB. In terms of getting sensitivities, a BAL should be done, but his question was, how long after initiation of 4-drug therapy would the BAL give a false positive. By false positive, I guess you could view that as as either afb negative, or culture negative (if the former represents dead TB bugs).
He was considering waiting 2 weeks to help decrease the risk to those in the bronchoscopy suite.
What do you think?
He was considering waiting 2 weeks to help decrease the risk to those in the bronchoscopy suite.
What do you think?
Tuesday, November 21, 2006
BCG and latent tb
A patient had a previous negative PPD as a requirement for work. She then went oversees for a time and receieved the BCG vaccine. She is now back in this country and as part of work requirements gets another PPD which is now positive. She is asymptomatic and the chest xray is negative.
How would you handle this?
How would you handle this?
Sunday, July 02, 2006
Follow-up to AFB
This was the 83 y/o man with no COPD, no TOB Hx with a respiratory tract infection with AFB growth from the sputum.
I ended up doing a combination of the suggestions from JJ and Jeff H: I hoped and assumed the AFB was not TB but with the positive PPD, and since I should not start just INH, I did initiate therpay with 4 drugs for TB.
The Cxs came back with a pan-sensitive MTb, ETH was discontinued and he is doing very well on RIF/PZA/INH.
Are you surprised at the paucity of symptoms and fairly benign CxR? I know Tb can present in many unusual ways but I like to see at least something abnormal with TB...
I ended up doing a combination of the suggestions from JJ and Jeff H: I hoped and assumed the AFB was not TB but with the positive PPD, and since I should not start just INH, I did initiate therpay with 4 drugs for TB.
The Cxs came back with a pan-sensitive MTb, ETH was discontinued and he is doing very well on RIF/PZA/INH.
Are you surprised at the paucity of symptoms and fairly benign CxR? I know Tb can present in many unusual ways but I like to see at least something abnormal with TB...
Tuesday, June 27, 2006
AFB

This 83 y/o man with no COPD, no TOB Hx was referred to us by his PCP for 2-3 days of cough and low-grade fevers at home. He had had a cold the week before with some rhinorrhea and then developed low-grade fevers (~100) at home with scant purulent sputum and dyspnea as well as malaise. No night sweats, chills, weight loss or hemoptysis.
His exam was only remarkable for B/L ronchi, worse on the right. On admission, he had the fairly benign CxR above; WBC ~9K with a left shift and no other biochemical abnormalities. He had minimal hypoxemia and was started on ABTx for a purulent tracheobronchitis with dyspnea in an 83 y/o patient. He had a great clinical response within the first 24 hours and was D/C'ed home off O2 in 2 days.
His sputum smears were non-contributory but 2 weeks later I got a call from our lab that he was growing AFB in his sputum Cx.
Would you assume it is TB or would you favor a non-TB mycobacteria? Clinically he was doing great at this time and had finished his ABTx (doxycycline). What would you do next?
Tuesday, March 28, 2006
Hemoptysis
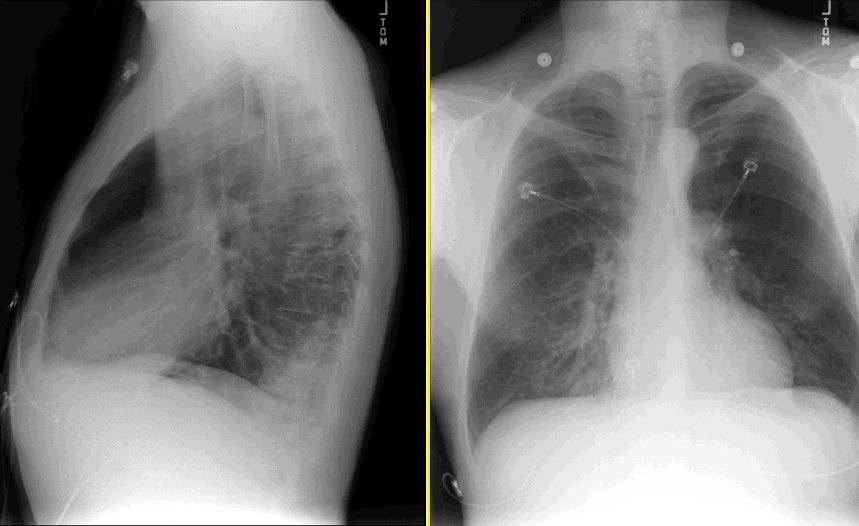
This is a 41 y/o man with a dramatic HIV Hx: he was diagnosed in '94 when he presented with PCP and a CD4 of 7 (!). He survived long enough to be started on HAART with a great clinical response. His most recent CD4 was ~260 though he still has a detectable viral load. His HIV infection was due to remote IVDA.
His course has also been complicated by CAD, previous AMI and CHF. He presented this time with acute-on-chronic R heart failure with increasing edema. He responded well to therapy but prior to D/C he developed a cough productive of bloody sputum and had the above CxR.
He is on his HAART (nevirapine, tenofovir and the lopinavir-ritonavir combo) and SMZ-TMP prophilaxis. He has a Hx of 2 negative PPDs.
Would you isolate him? How would you treat him?
Subscribe to:
Posts (Atom)