Redneck Crit Care (nice name) submitted this question:
One of our CT surgeons has been using Precedex for postop sedation for vent patients with good success.
www.ptjournal.com/ptjournal/fulltext/30/3/PTJ3003158.pdf
according to information in that article, it appears to be a very attractive option. It is a short-acting alfa2 agonist and you do not have to discontinue this before, during or after extubation because it does not cause respiratory depression. Are many intensivists already using this in medical ICU?
Showing posts with label Critical care. Show all posts
Showing posts with label Critical care. Show all posts
Monday, October 15, 2007


Wednesday, February 07, 2007
C. diff, C. diff run, run diff run
This is more of a critical care (or general care, if you will) than true pulmonary.
I have been seen a lot of docs (including some ID) treating uncomplicated C. diff colitis with PO vanco up front instead of Flagyl. Have recommendations changed? Do you use much PO vanco?
I have been seen a lot of docs (including some ID) treating uncomplicated C. diff colitis with PO vanco up front instead of Flagyl. Have recommendations changed? Do you use much PO vanco?
Tuesday, November 07, 2006
ICS in the hospital
What is your usual practice regarding inhaled steroids when you admit a patient for either status asthmaticus or AECB?
If they are already on an ICS on admission and they will be on a systemic steroid do you continue the ICS?
Conversely, if they are not on an ICS on admission and are now on a systemic steroid, do you start an ICS during the admission or after D/C?
If they are already on an ICS on admission and they will be on a systemic steroid do you continue the ICS?
Conversely, if they are not on an ICS on admission and are now on a systemic steroid, do you start an ICS during the admission or after D/C?
Friday, September 29, 2006
Sepsis and steroids
IS:
This is not a case presentation, but want to take a poll on what people are doing about steroids and sepsis. Do you administer steroids emperically after initial fluid bolus or do you attempt resuscitation per the 6hr bundle first and then administer steroids if still on pressors or hypotensive?
This is not a case presentation, but want to take a poll on what people are doing about steroids and sepsis. Do you administer steroids emperically after initial fluid bolus or do you attempt resuscitation per the 6hr bundle first and then administer steroids if still on pressors or hypotensive?
Tuesday, September 26, 2006
Hemodynamics
A patient intubated and sedated for hypoxia (history of aspiration although CXR negative) had initial swan numbers of: CO 5 L, CI 3.24 PAP 26/16. PCW 8 with cvp of 4. SVR 1362. PVR is 190. AFter fluid boluses with no change in CO, PCW still 8 with a CVP of 6. His SBP has been 116/78 basically unchanged throughout. After fluid blouses he is now about 10 L up with really no change in the above swan readings or bloodpressure. How would you interpret this? Of note a surface echo showed an EF of 25-35%.
Here's his cxr.
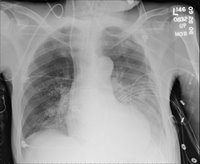
Here's his cxr.

Monday, August 21, 2006
Anemia
This is more of a critical care than pulmonary question. It came up today in discussion with renal...
The gold satndard for iron-def. anemia has been staining the bone marrow for iron stores. Nobody does that much anymore as first test since ferritin has such a good correlation with iron stores. The discussion was whether you can have iron-deficiency anemia with good normal ferritin (not normal-low, low-normal, borderline, etc.). Even though ferritin is an acute phase reactant and may mak a borderline ferritin level seem normal it shouldn't push it to the mid-high range. (ferritin will roughly triple as an acute phase marker, Ann Rheum Dis 1986 Jul;45(7):596-602)
Do you look at the iron/iron sat or do you trust the ferritin?
The gold satndard for iron-def. anemia has been staining the bone marrow for iron stores. Nobody does that much anymore as first test since ferritin has such a good correlation with iron stores. The discussion was whether you can have iron-deficiency anemia with good normal ferritin (not normal-low, low-normal, borderline, etc.). Even though ferritin is an acute phase reactant and may mak a borderline ferritin level seem normal it shouldn't push it to the mid-high range. (ferritin will roughly triple as an acute phase marker, Ann Rheum Dis 1986 Jul;45(7):596-602)
Do you look at the iron/iron sat or do you trust the ferritin?
Thursday, August 17, 2006
Failure to wean
This is a 44 year old man with DM, s/p renal transplant several years ago. He has the other associated micro- and macro- vascular problems associated with DM, including severe PVOD and a non-healing, chronic LE cellulitis for which a BKA has been recommended (but refused--he is on chronic supressive antibiotics). His immunosupression includes cyclosporine and prednisone.
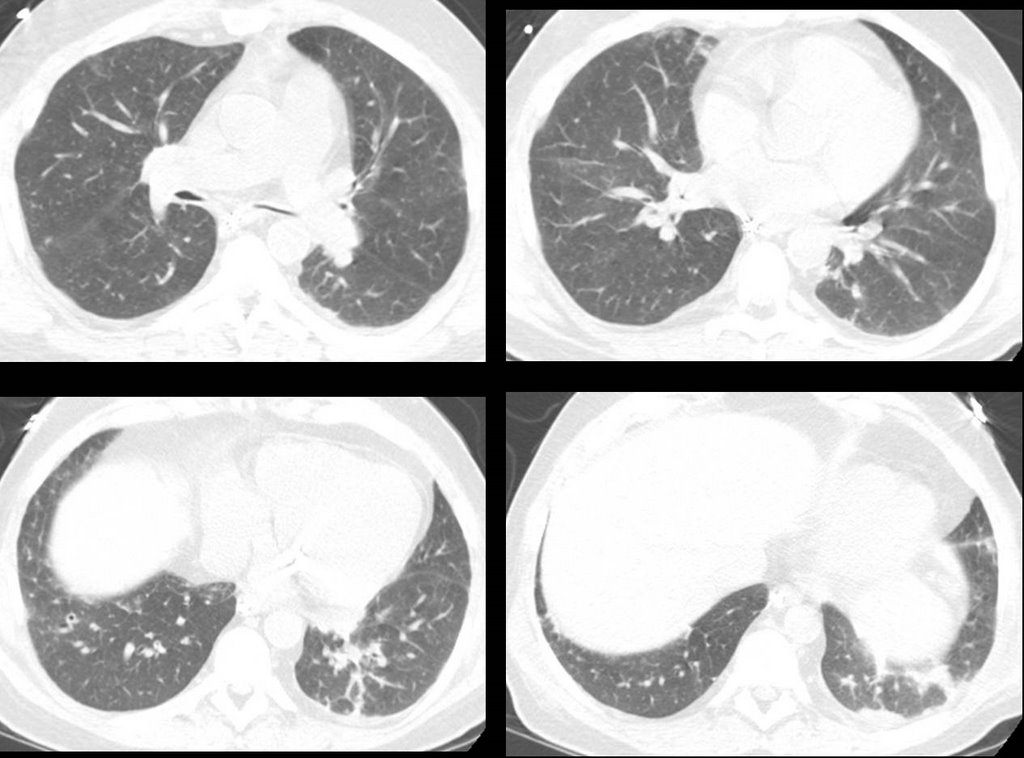
He was admitted to the ICU with hypoxemic respiratory failure requiring intubation for what turned out to be herpes pneumonitis, and was treated with a 21 day course of acyclovir. Over this course, he was easily ventilated and oxygenated with progressively improving respiratory parameters. On two occasions, his weaning parameters were excellent, and he easily tolerated minimal ventilatory support (PS-5/PEEP 5) for 2 hours. Each time, he required re-intubation for respiratory distress several hours after extubation.
Here's some representative cuts from a CT scan done about 10 days into his hospital course.
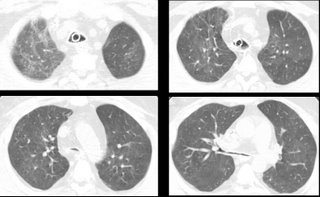

He was admitted to the ICU with hypoxemic respiratory failure requiring intubation for what turned out to be herpes pneumonitis, and was treated with a 21 day course of acyclovir. Over this course, he was easily ventilated and oxygenated with progressively improving respiratory parameters. On two occasions, his weaning parameters were excellent, and he easily tolerated minimal ventilatory support (PS-5/PEEP 5) for 2 hours. Each time, he required re-intubation for respiratory distress several hours after extubation.
Here's some representative cuts from a CT scan done about 10 days into his hospital course.

Thursday, June 01, 2006
FACTT trial
The NEJM published results from the FACTT trial on the 5/25 issue: "PAC-guided therapy did not improve survival or organ function but was associated with more complications than CVC-guided therapy."
Had you been using PACs often for management of ALI/ARDS and do you think this will further change your practice?
Had you been using PACs often for management of ALI/ARDS and do you think this will further change your practice?
Thursday, April 27, 2006
PEEP
Today's NEJM's cover article is by Gattinoni et al and they have looked at the ammount of "recruitable" lung in the setting of ARDS. This is after the results from the ALVEOLI study on High-Low PEEP.
How do you use PEEP in your ARDS patients? Have you been trying to "recruit" more lung with higher PEEP? Since the patients on the High PEEP did not have worse outcomes are you more comfortable with higher PEEP when oxygenation is a problem?
How do you use PEEP in your ARDS patients? Have you been trying to "recruit" more lung with higher PEEP? Since the patients on the High PEEP did not have worse outcomes are you more comfortable with higher PEEP when oxygenation is a problem?
Monday, April 17, 2006
Percutaneous trachs
Have you had much experience or come across data on percutaneous (vs open surgical) trachs in you persistent respiratory failure ICU patients?
Friday, March 17, 2006
Respiratory failure
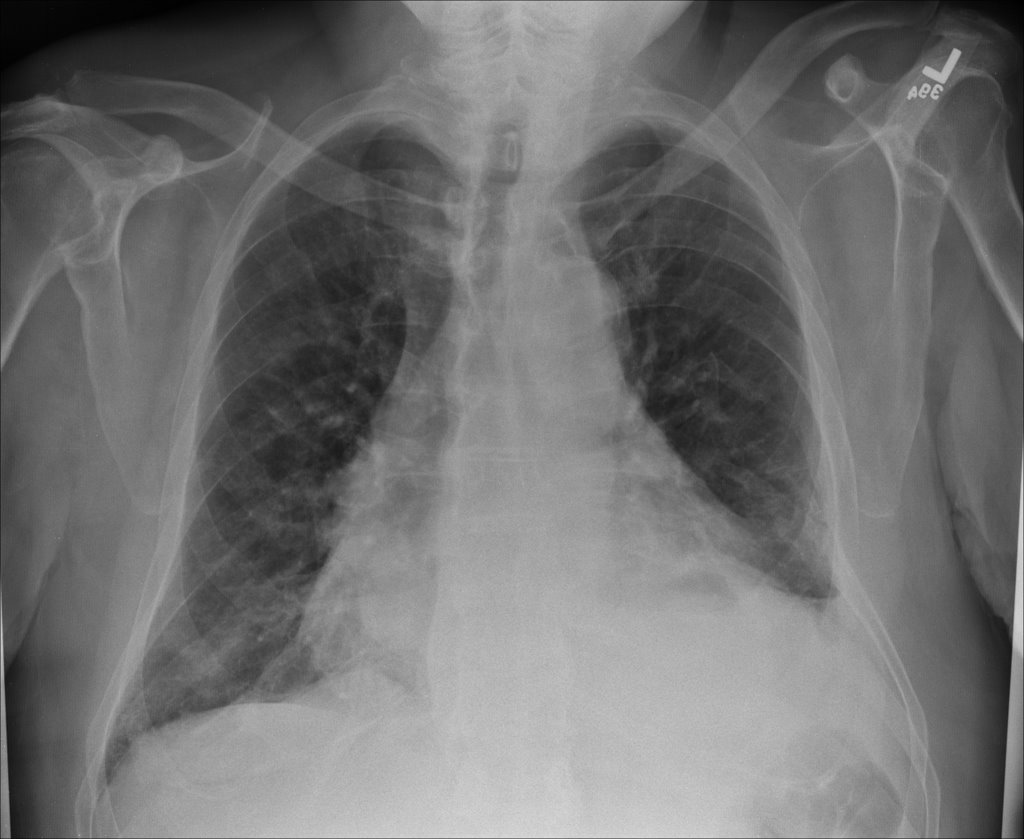
60 y/o man PmHx only ITP (controlled with prednisone 40 qd), and hypertension. He had 6 months of SOB, and was found to have severe AI. He underwent valve replacement. His preop CXR is here: 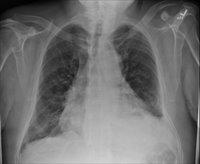
He then developed SIRS (WBC, fever, tachy) but no infectious source ID'd. He was intubated. A CT is here: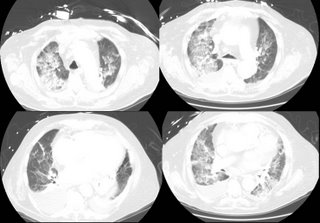 .
A month later he is still intubated with the following CXR: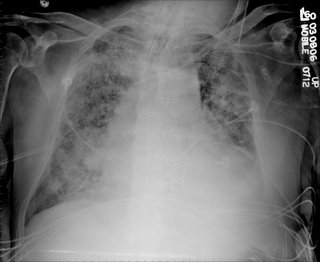
What is your differential diagnosis? What tests/procedures/other data would you like to know?
He then developed SIRS (WBC, fever, tachy) but no infectious source ID'd. He was intubated. A CT is here:
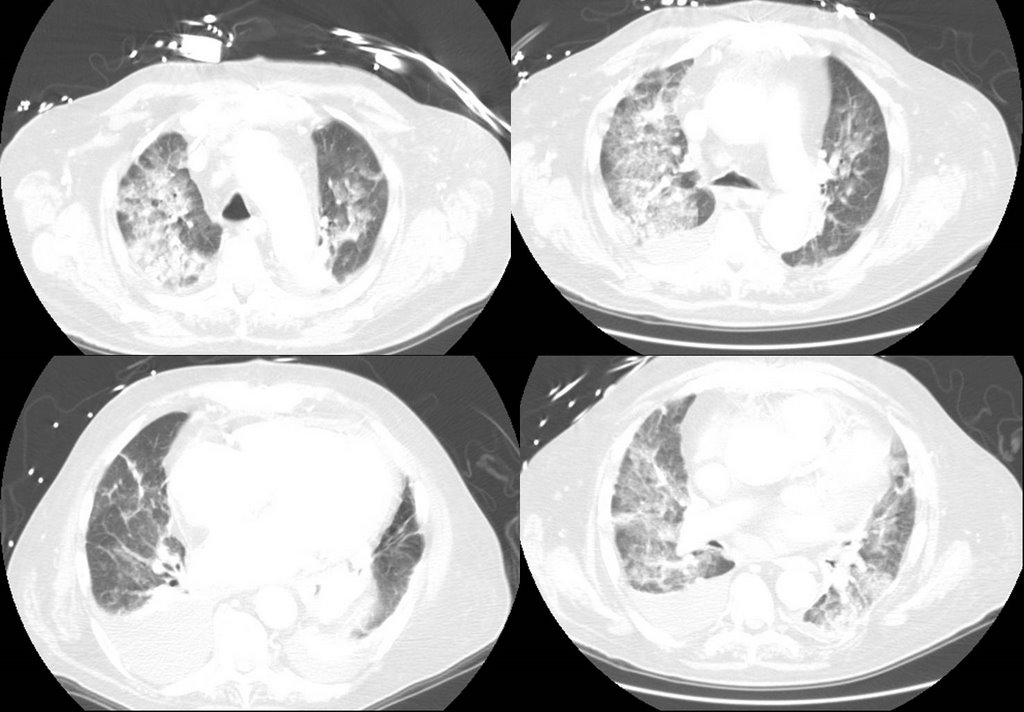 .
A month later he is still intubated with the following CXR:
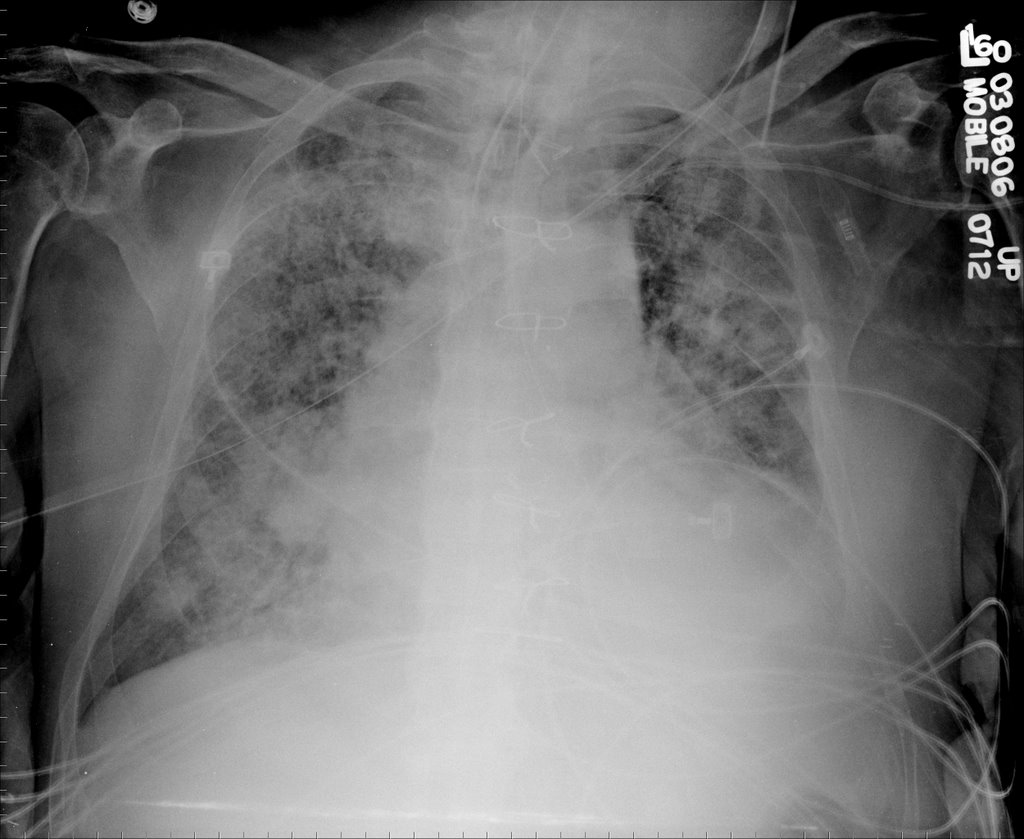
What is your differential diagnosis? What tests/procedures/other data would you like to know?
Thursday, March 16, 2006
Shortness of breath
This man has significant alcohol abuse and came in with severe shortness of breath. He was intubated after this chest xray.

What do you see and what next?
Answer here
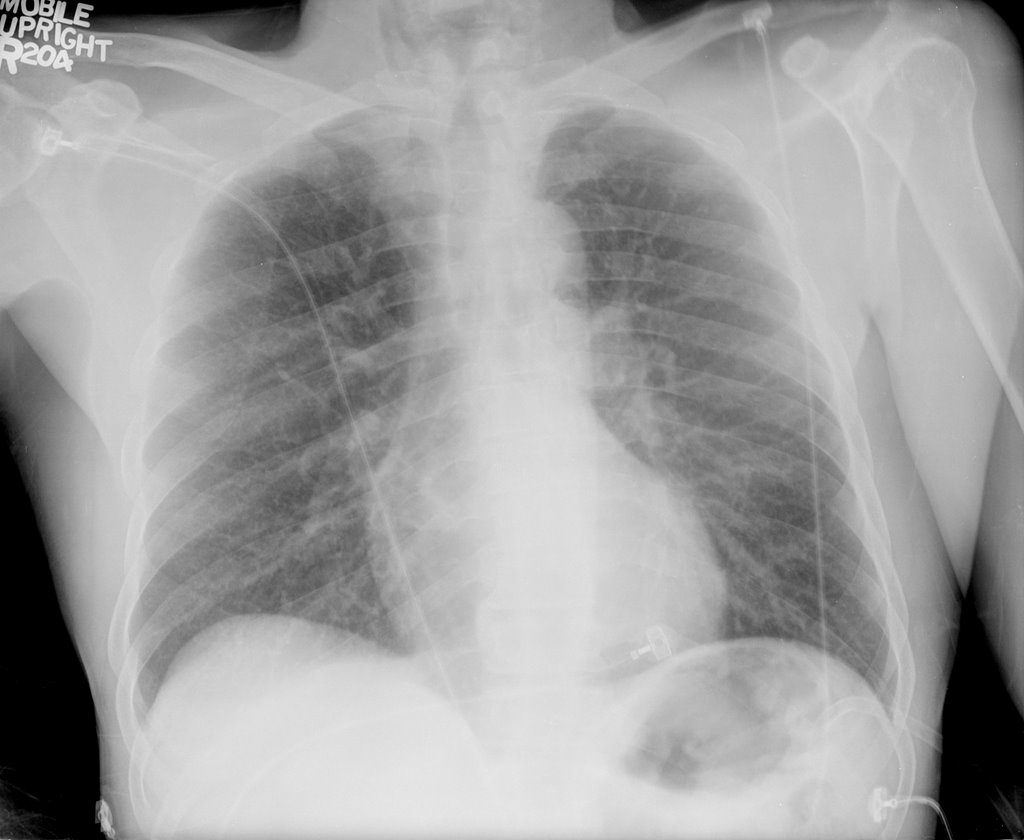
What do you see and what next?
Answer here

Subscribe to:
Posts (Atom)