Showing posts with label ILD. Show all posts

Thursday, March 20, 2008

Acute ILD

This 77 year old man has had a bit of honeycombing at the bases since at least 2004. Radiographically c/w UIP. Biopsies not done and he has been stable for years (and FVC normal at 84% predicted).
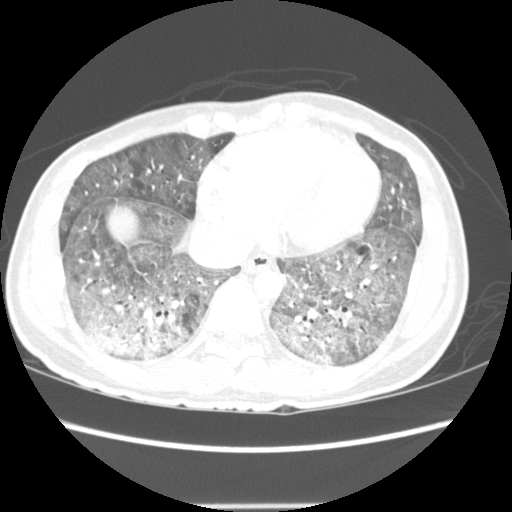
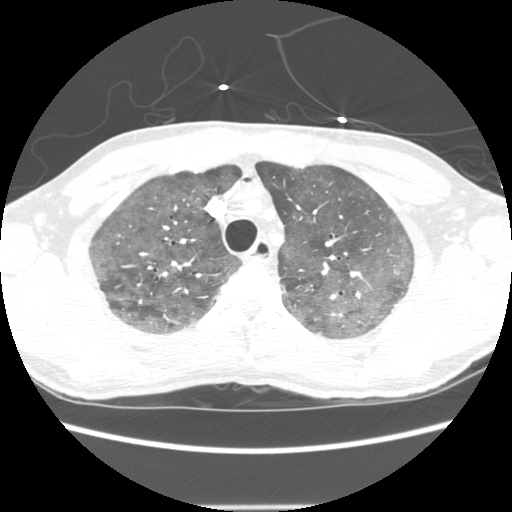
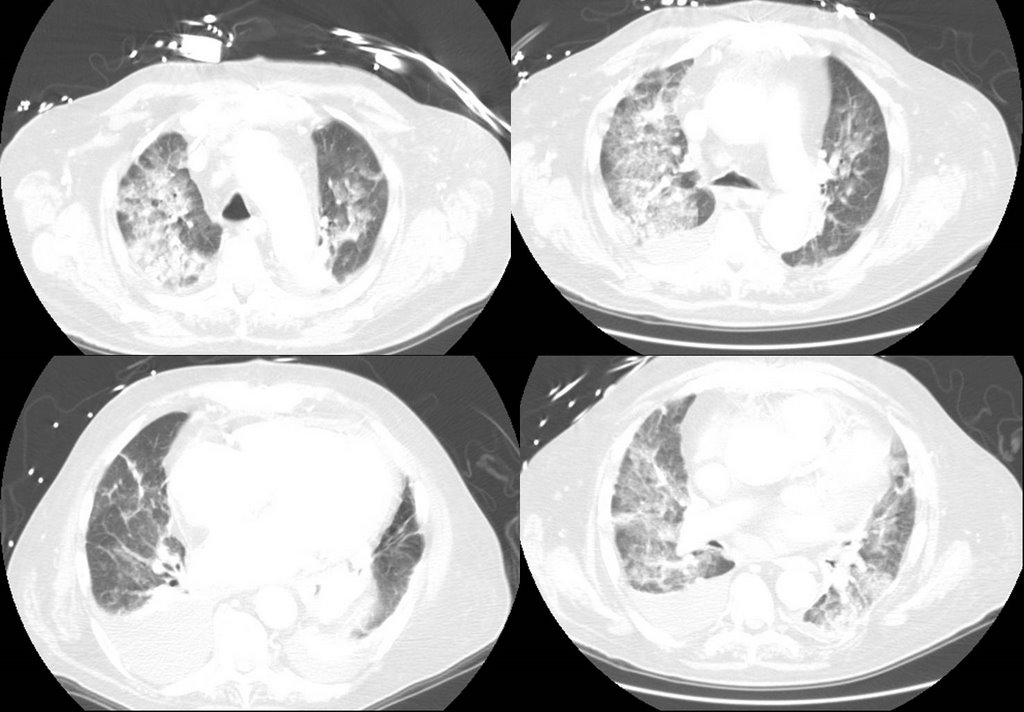
In February he developed worsenign cough and SOB. He was admitted and was hypoxic with the CT shown below. A cath was done showing normal wedge, normal CO/CI.
A BAL showed only 184 cells half of which were macrophages. A TBBX was not done because he's on coumadin for afib and we didn't think it would add much to determining the diagnosis.
SH, desk job all his life. In January, routine maintenance change of the humidifier pipes in his furnace. This may be a red herring but throwing it out there. No one else in household sick.


Was going to send him for open lung/VATs, but what do you think are possible etiologies?
I also repeated autoimmune chemistries that had been negative in 2004.

Friday, February 15, 2008

Fibrosis

A submission from a reader: "34 year old, non-smoking African American female presenting with a recurring (for three years now), chronic (lasts for several weeks up to a few months) dry, non productive cough. No other symptoms (though the attached CT report says wheezing). No response to a variety of drug treatments over the years, including steroid shot, Levaquin, OTC Mucinex, OTC Claritin, Tussionex, Nasacort, OTC Prilosec, 6-day regimen of Metrol (4mg), Advair and Albuterol. First pulmonologist (who performed no diagnostic tests) diagnosed asthma and allergies. Nothing indicated on chest x-ray. Internal medicine doctor ordered CT scan (report attached). Second pulmonologist said subpleural cysts exist, which he indicated exist with UIP patients, but he said this was not UIP. Also said it's not tuberculosis or sarcoidosis. Prescribed 20 mg of Prednisone twice a day to get rid of cough, said we will proceed once cough is gone. Said a lung biopsy or thoracic biopsy may be in order.

CT reading:
Helical CT images through the chest were obtained following
intravenous contrast administration.

Within both lungs and involving both the upper and lower lung zones,
there are areas of subpleural macrocystic change with some
associated subpleural interstitial thickening. There are no
particular areas of ground-glass opacity associated with these
findings. No significant nodularity is seen. The central and midlung
zones are spared. No pleural fluid or lymphadenopathy is seen. These
findings can be seen in patients with usual interstitial pneumonia
(UIP) although this would be somewhat atypical in a patient of this
age group. Does the patient have a smoking history? Other
interstitial lung disease in its early stages may give a similar
appearance.

Tuesday, October 23, 2007

IPF treatment - worse than the "cure"

Here's another anecdote on a patient started on prednisone/azathioprine/NAC for IPF. He was started on this for a variety of reasons, but one was that the biopsy had a bit more inflammatory changes even though there was ample fibroblastic foci and heterogeneity, so I thought a 3-6 month trial would be reasonable. By the time his imuran was up to 75 mg, I saw him. A repeat spiro was unchanged (FVC 43% predicted) but his DLCO went from 35% to 45% so I continued the meds. However he had mouth pain and the tongue showed possible thrush so I kept the Imuran at 75, gave some nystatin swish and sent him out to be followed up in 2 months and repeat the HRCT with the sprio/DLCO. However, his mouth pain did not go away and worsened, and he started developing malaise and a fever. I saw him in clinic that day. He looked fairly sick but vitals ok. He had a soft palate lesion. I got derm to KOH it and there are some non-budding hyphae so he's to get clotrimazole . Then almost as an afterthought I added on amylase and lipase to the repeat LFT's and low and behold the lipase is 800.
Of note his WBC was 13 and now down to 6....
This side effect is likely going to be self-limiting as he stays off the imuran. As I tell him to go light on PO intake, I am adding a creatinine to make sure he is not volume depleted (he's an outpatient).

Tuesday, September 18, 2007

Pneumosiderosis

What causes Pneumosiderosis? Try doing a search on that you won't find anything.
It is a 64 year old patient presenting with some weight loss and a bit of a dry cough. CT showed bilateral reticulonodular opacities and no lymphadenopathy. We sent him for a bronch to assess for things like MAC. The TBBx came back as Pneumosiderosis (iron in the lung). The micro was negative. He was a welder as an occupation. The metal was steel.

Wednesday, March 21, 2007

Rheumatoid arthritis and effusions

From one of our readers. Edited a slight bit.

Found your site and thought I‘d run some of this by you to get your take on the situation so we might be more well-equipped to talk to our local doctors.

Husband is a 52 yr old smoker (about a pack and a half a day) with advanced rheumatoid arthritis. He is on:
Methotrexate for ten years (20 mg a week, currently)
Had a five-year stint on enbrel/etanercept - discontinued six months ago)
Recently moved to remicade.
Other meds: folic acid, indomethacin, prednisone 30 mg, QD, and hydrochlorthiazide (12.5 mg, daily).

February 2005, he started feeling “full” in his torso. Blood tests were “normal”. But he gained 9 pounds in a day. In the ER he was fpund to have fluid around his heart and in his pleural cavity. They withdrew 31 ounces of fluid off the heart. All seemed well....for a time.

Had another bout with all this in March, 2005.

Around Christmas 2005, he started feeling full again, and the doctor said go to the Emergency Room. Hubby said he didn’t want to go through all that again, so they told him to take prednisone (40 mg a day). Gave him relief. Started to step-down the dosage of prednisone...got down to 10mg/day, and started feeling full, again.

HRCT was ordered and showed:

Clinical Information: Pleural effusion.

Findings: Standard and high resolution chest CT images demonstrate moderate centrilobular and paraseptal emphysema. No focal consolidating process. Mild ground glass with traction bronchiectasis involving the peripheral aspect of the lung fields, with upper lung zone predominance. The findings are nonspecific, and may represent sequela of chronic hypersensitive pneumonotis. There is evidence of prior granulomatous disease. There is a 5-mm hyperdense pulmonary nodule in the right upper lobe; this nodule may be partially calcified. There is also an 8-mm, not obviously calcified nodule in the right middle lobe. Small left and trace right pleural effusions are noted. There is no lymphadenopathy. The heart is not enlarged. There is not significant pericardial effusion. The adrenal glands are not enlarged. There is a focal 3-cm mass lesion involving the pancreatic tail. The lesion demonstrates slightly higher attenuation relative to the remaining pancreatic parenchyma. Central low attenuation is noted, suggestive of cystic components. No significant surrounding inflammation is identified. There is not pancreatic ductal dilatation.


I have been reading as much as I can to try and understand what this means. Originally, when I started research, I had not began with the idea that all of these are tied to his rheumatoid arthritis; however, the more I read, a correlation seems to be drawn between many of these conditions and either rheumatoid arthritis, or prolonged exposure to methotrexate.

I had read one of the posts on the pulmonaryroundtable.com site title BAL eosinophilia in a patient with rheumatoid arthritis which seemed to resemble some of my husband’s case.

I wanted to ask what you thought of these results and to see if you thought that my supposition / correlations drawn in my own mind are simply that (suppositions on my part), or if you think that these links are founded, possible, and real.

I am also concerned about the noted lesion on the pancreas, as I do not seem to be able to find much regarding pancreatic mass lesions. It is very confusing reading

Monday, March 05, 2007

Interferon-gamma trial for IPF is discontinued

Well, the press-release was today so it is public info: the phase 3 trial testing IFN-gamma vs. placebo in patients with IPF has been discontinued. The independent data monitoring committee did an interim analysis and found no difference between IFN-gamma and placebo for mortality (14.5% in the Actimmune group as compared to 12.7% in the placebo). The adverse reactions were consistent with prior clinical experience(constitutional symptoms, neutropenia and possibly pneumonia).

“The interim results of the INSPIRE trial and our decision to discontinue the trial are disappointing,” said Steve Porter, M.D., Ph.D., Chief Medical Officer at InterMune.

I'm not sure what this means for the company, but they are also running the perfenidone trial, but not so sure this will fare any better...

To me, this is not so surprising, but it really does illustrate the importance of being careful not to read too much into sub group analysis before the next study is done- the original study found that patients with more "mild" IPF (FVC 55-90% predicted) might have a survival advantage and the current study was powered to test that hypothesis. Ultimately it was found not to be the case after all.

People currently taking the IFN-g as part of the study will be instructed to stop it, and everyone will then pack up their bags and move on to the next latest and greatest...

Does anyone have any patients enrolled int his trial?

Tuesday, January 09, 2007

Hypersensitivity Pneumonitis

Anonymous M.D. asks if anyone knows of alternative immunotherapy for the treatment of chronic hypersensitivity pneumonitis in a patient who is not responding to steroids. Her FVC has remained in the mid 50% range regardless of predxnisone does (range 0 to 40 mg). The HRCT shows fairly extensive ground glass to indicate an active alveolitis. Of note, this patient has an open lung bx that was consistent with the diagnosis of HP).

Monday, December 11, 2006

Differential and w/w

43 year old presented with 6 weeks of progressive dyspnea associated with URI-type symptoms. Had recieved several courses of antibiotics as an outpatient. No fever/chills. + non-productive cough. No associated s/s. Non-smoker. No occupational exposure. On presentation, he was hypotensive, but alert and oriented. His was quite comfortatble despite profound hypoxia (initial oxygen saturation of 62% on room air). Physical exam has some scattered rales. WBC is 4, without a shift. Blood count and platelets are normal. He is hypoxic, requiring up to 100% supplemental oxygen by non-rebreather to maintain a pO2 in the 60's. His ventilation is adequate, with a pCO2 of 42 and a pH of 7.39.

A CT scan shows:


Saturday, December 09, 2006

Follow-up to Pulmonary Nodules

This is the 51 y/o woman with COPD and pulmonary nodules.
We had the same concerns and DDx as proposed in the discussion. I did a bronchoscopy and we got good samples consistent with RB-ILD.
She was counselled again regarding TOB cessation and agreed to try varenicline. She will follow-up in a few weeks and we will monitor her CxR and PFTs.

Friday, November 24, 2006

Follow-up to dyspnea

This is the recent post of the 47 y/o woman with dyspnea. JJ and Krayem suggested HP and on the TBBx we had loose granulomata with lots of lymphocytes and negative organisms on stains and Cxs. The pathologist felt quite confident calling it as HP. Unfortunately I don't know what is the culprit exposure yet...

Wednesday, October 04, 2006

Dyspnea and a LUL mass

Here's a case from Arenberg:

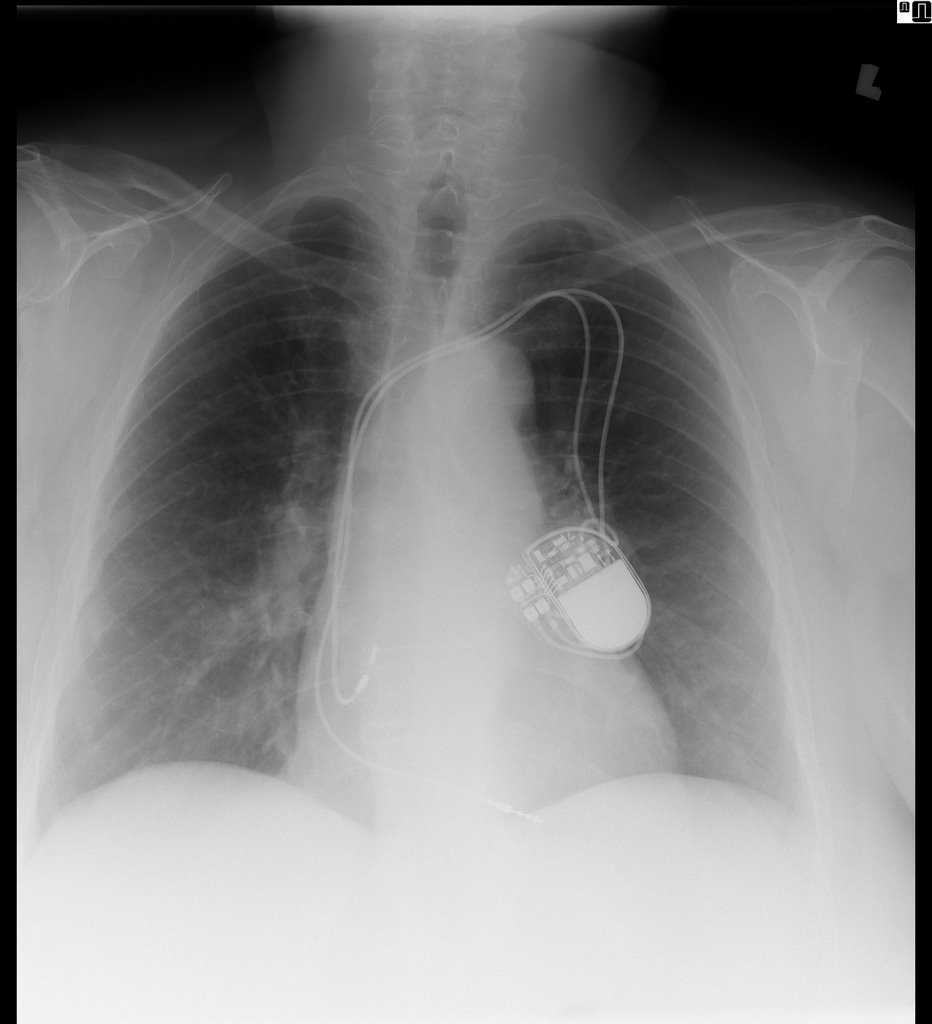
This is 69-year-old lady with coronary artery disease, diastolic congestive heart failure, and dyspnea on exertion. She came to see me because her cardiologist said she has been experiencing increased dyspnea out of proportion to her normal symptoms for ~3 months. Other than a pacemaker over her left chest, her plain chest x-rays were normal

and her pulmonary function tests were mildly restrictive (FVC ~69%), actually improved from her last testing ~ 4 years prior.

I got a VQ scan that was normal, but only on her second visit (when I actually asked) did I learn that she has had 2 birds as house pets for the last 3 years. She further revealed that she has felt unwell going back about 2-1/2 years. One of the birds was in fact sick, and during this time, she fed the bird from mouth to mouth. Yes, I am serious. She was DEAD SET against getting rid of the birds, so I got a CT scan in anticipation of doing a bronch, to prove she had HP.

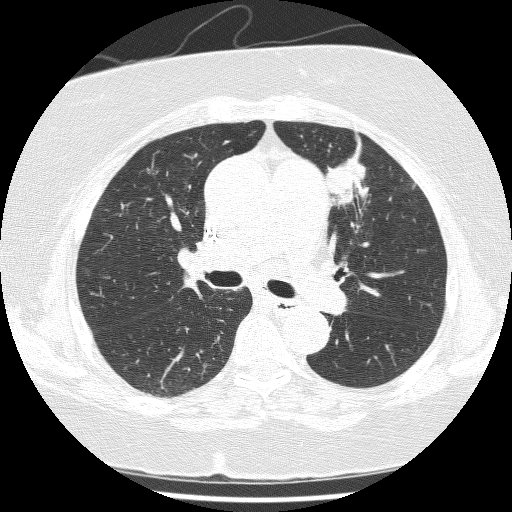
The CT showed very subtle changes of ground glass, and was actually read as no evidence of ILD, but surprise surprise, she now had a LUL mass that was not seen on the CXR taken 2 months earlier. The radiologist thought it was likely to be inflammatory. What would you do?

I have more images, and some cool pictures to follow, but I’ll hold onto them until people have a chance to comment.


--------------------------
UPDATE:
"...good evidence for chronic HP in the form of a patchy chronic
bronchiolitis that includes occasional multinucleated giant cells of the
sort commonly seen in that condition"

Comments from our pathologist.

Monday, July 24, 2006

More on the woman with eosinophilia

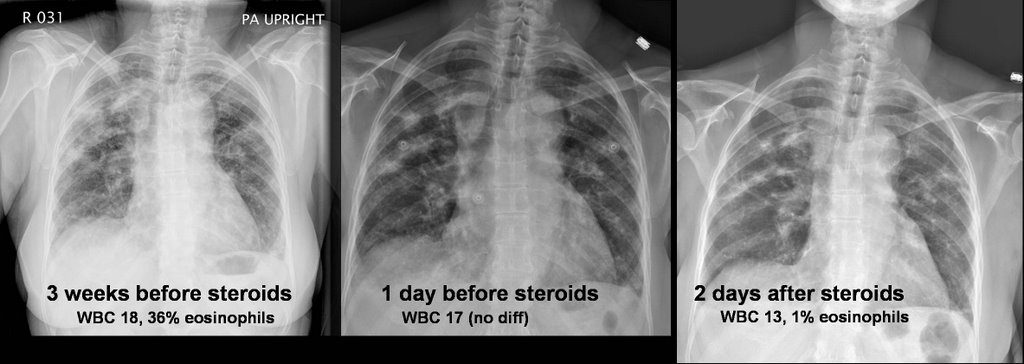
Well, as you might remember, this patient with a past medical history of asthma had had a few months of dyspnea and malaise. A peripheral showed 42% eosinophils and a BAL showed 20% eosinophils. A transbronchial biopsy showed eosinophilic infiltration. Micro was negative. Stool O&P was also negative.
She was given steroids with subjective improvement. However, I am not entirely satisfied with a diagnosis of chronic eosinophilic pneumonia. Here are her radiographs:


Now her amylase and lipase are elevated which does not go with eosinophilic pneumonia, and I don't have a good reason for that. Any thoughts out there? If it is parasitic, at least she is not worsening on the steroids....

Monday, July 03, 2006

RA-associated lung disease

A 68 y/o woman with a long-standing history of Rheumatoid Arthritis and Sjogren's Syndrome (well controlled on Prednisone 7.5mg QOD, never used a steroid-sparing agent), was referred with mild but progressive dyspnea on exertion for several months.

Full pulmonary function studies show an FEV1 of 2.38, which is 102% of predicted. The FVC was 3.22 or 100% of predicted. The FEV1/FVC ratio is 74%. Total lung capacity is 101% of predicted and residual volume is 104% of predicted. The DLCO is decreased at 51%. This is unchanged from PFT's 18 months ago, with the exception of the decrease DLCO from 57%.

An HRCT (not available to upload), showed:
"Bilateral basilar predominant groundglass opacity with smooth septal
thickening. There are areas of lobular spareing.
A few well-defined scattered thin-walled cysts are present
No intrathoracic lymph node enlargement."

A subsequent bronchoscopy with BAL showed no evidence of infection. The differential had 42% lymphocytes, and 54% histiocytes. Transbronchial biopsies were read as: "Chronic and granulomatous inflammation. Amorphous acellular material. Congo red stain negative for amyloid. GMS stain for fungal organisms negative."

Question: How should one approach this case? Would you take the CT scan, the lack of infection on BAL, and the lymphocytosis on BAL and treat with a presumptive diagnosis of RA-associated NSIP by increasing the steroid dose? Or would you proceed with a surgical lung biopsy. Any other thoughts?

Tuesday, May 09, 2006

PCP prophylaxis

User submitted question:

A patient of mine has RA-ILD and is on methotrexate. She will be on it for at least 3 months (or longer if it works). Do you prophylax for PCP with Bactrim in this case?

Monday, March 27, 2006

Rapidly progressive fibrosis

67-year-old woman with progressive shortness of breath since September. No cough, fevers chills night sweats.
Past medical history is significant for coronary artery disease, status post MI 11/2005, hypertension, diabetes, breast cancer 7/2004(5-FU,cytox, Mtx) s/p xrt, and chronic renal insufficiency.
SH; ex smoker. Occupation: Did military work.
meds: CAD meds and some inhalers etc.
Over the last few months her dyspnea worseneed and she is now on 6 L of oxygen 24/7.
Here is a CT from last month:

What do ye all think is going on?

Friday, March 17, 2006

Respiratory failure

60 y/o man PmHx only ITP (controlled with prednisone 40 qd), and hypertension. He had 6 months of SOB, and was found to have severe AI. He underwent valve replacement. His preop CXR is here:
He then developed SIRS (WBC, fever, tachy) but no infectious source ID'd. He was intubated. A CT is here: .
A month later he is still intubated with the following CXR:

What is your differential diagnosis? What tests/procedures/other data would you like to know?

Friday, March 03, 2006

The IPF discussion continues

As there have been several new cases since Jenning's recap, I wanted to make sure that the insightful comments by jgiustino did not get lost in the fray. Link through the heading of this post to see the discussion and comment further.

Monday, February 27, 2006

IPF recap

I thought it would be fun to highlight some of the previous cases. This is also useful because occasionally we'll get a comment long after the case was posted so it may get lost as new cases bump the old ones back.

Recently there was some interesting discussion about the treatment for IPF. There was the article on Acetylcysteine and pulmonary fibrosis (IPF). More often than not, we read a high impact journal and take what it finds at face value. As busy physicians we might not have the time or patience to read an article critically, and we sometimes "trust" that the peer reviewers read it critically for us. This may be especially true in a high impact journal like the New England Journal of Medicine. It seemed like a straight forward question: "where do I get acetylcysteine to prescribe for my patents?" But the comments highlight the fallacy of believing everything we read. As Jeff H pointed out, I think it's critical to point out that NAC was used IN ADDITION to Azathioprine and Prednisone. There are no trials that have evaluated NAC as monotherapy. Moreover, there was no "placebo" group included in the NEJM paper. So, there are NO DATA that oral NAC, as monotherapy, is any better (or worse) than nothing. Doug (and others) highlighted this, pointing out that NAC may have merely had a protective effect on the harmful effects of prednisone. And jgiustino's comments are interesting: All I can say is that this was a bad study! The data from patients that actually completed the study did not show ANY significant change in lung function between the two groups. The authors then needed to resort to "last observation carry forward" to show significance ....this is a highly controversial statistical method. I am very surprised that this has not been questioned by more people. I think that this study proved that NAC prevent bone marrow toxicity from imuran (they did not need "last observation carry forward" to prove this. All else is very suspect as far as I'm concerned and I wish they had the foresight to get a larger patient population into the study so they would not have to resort to such statistical games.


The diagnosis of UIP can also be challenging. What's more important, a biopsy showing UIP or typical CT findings of honeycombing at the bases with minimal ground glass? What about a biopsy with UIP and previous CTs showing LOTS of ground glass? I posted a case where a patient had an open lung biopsy that was consistent with UIP but with chest CT's back 6 years showed that there has been lots of ground glass (and upper lobe to boot). My question was, does the biopsy trump the atypical CT findings, OR do the previous CT findings make us question the assumption that UIP makes the diagnosis of IPF? I'm not sure the question has been adequately answered but the comments shed some light on the controversy. More than one pointed out that the diagnosis of UIP is also dependent of the pathologist.
And if we have a diagnosis of UIP by biopsy, would we withhold treatment with immunosuppressives? What if the pathologist read it wrong and it is truly a steroid-responsive disease? One commented that this is also the best argument on why we should "treat" our UIP patients with a 3 to 6 month course of prednisone and imuran..not to treat UIP but to definatively rule out other treatable diagnosis."

So the same research group showing that UIP trumps all other biopsy specimens (in terms of prognosis) also found that the dignosis of UIP is pathologist-dependent. In other words, if you are not at a major university specializing in IPF, ignore the biopsy report and treat everyone with prednisone for 6 months to see if they get better!

But seriously, it sure is strange that a pathologist would have difficulty with the diagnosis. After all, all you need is a biopsy showing fibroblastic foci, areas of normal parenchyma, areas of fibrosis and honeycombing in the periphery, and a paucity of inflammatory cells. What's the problem?

Monday, February 20, 2006

IPF?

A patient with shortness of breath. An open lung biopsy in 2002 was consistent with UIP:

Interstitial fibrosis predominantly distributed peripheral subpleural areas of the bx. Also multiple foci of active fibrosis. Also foci of reactive pneumocytes and expansion of some of the airspaces with incipient honeycomb formation. Occasional foci of mild non-specific chronic inflammation and also foci of alveolar cells/macrophages within airspaces. Areas of normal lung parenchyma interspersed within the fibrotic foci. No granulomas. Grocott stain negative. The overall histologic picture is in keeping with usual interstitial pneumonia (UIP).

But here are the CT's:
1999: "Multiple patchy opacities in the right upper lobe with one more nodular appearing opacity seen on images 16-18 are of uncertain etiology. Scattered unenlarged lymphadenopathy and one single borderline enlarged subcarinal node is seen. Inflammatory ( BOOP, MAI, etc. ) cause is more likely but malignant etiology should be excluded.

later in 1999:Multiple patchy & nodular lesions completely (or nearly) cleared. Several ill-defined opacities remain. Resolving inflammatory disease is suspected. Multiple non-enlarged mediastinal LNs, including AP window, low right paratracheal, right tracheobronchial, and subcarinal lymph nodes, are unchanged.

2002: Thickening of the interlobular septa and honeycombing peripheral and basilar distribution. In addition, bronchiectasis is present in the lower lobes and ground glass appearance persists, more predominant in the lower lobes.

So we have a biopsy with "UIP" (RML and RLL open lung, done after the above HRCT and after a nondiagnostic bronchoscopy). Is anyone bothered by the previous CT's suggesting an inflammatory look to it (i.e. ground glass)? In my opinion this is a previous inflammatory process (perhaps NSIP, BOOP, HP, etc) that has progressed to fibrosis; do you feel that the biopsy showing foci of fibroblasts represent true idiopathic IPF?

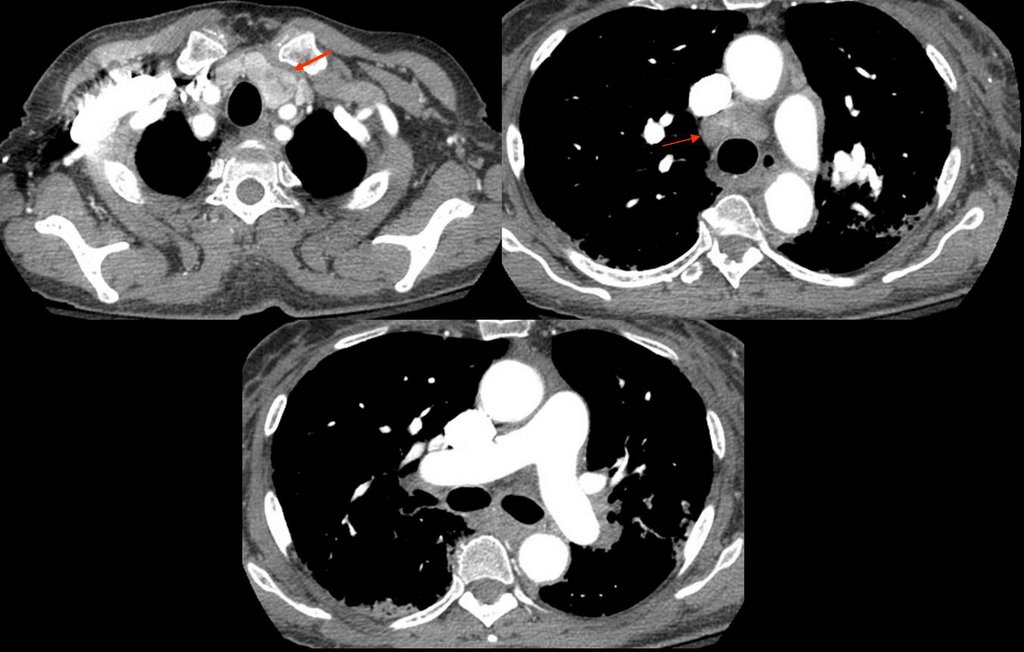
Shortness of breath over a 2 month period

This 50 y/o AA woman presented with shortness of breath. Without further history, what would be your (not necessarily complete) DDX based on the CT. Also note the mediastinal nodes (arrows).