One of my COPD patients was asking me about purchasing a portable/travel concentrator such as this one.
Have you had much experience or feedback with portable oxygen concentrators?
Showing posts with label COPD. Show all posts
Showing posts with label COPD. Show all posts
Wednesday, December 27, 2006


Wednesday, October 25, 2006
Preop eval for secondary HTN due to severe COPD
Redneck pulmonologist submits this question:
Would you do anything for secondary pulmonary hypertension (estimated PAP of 80-90 mmHG on echo) due to COPD before undergoing renal transplant? Her COPD is 2 to AAT deficiency and stable on AAT replacement. FEV1 of 40% predicted. She has documented nocturnal desat on sleep study without significant sleep apnea. But she is non-compliant with home O2. Daytime sat on RA is OK. She is not a smoker. She is on dialysis and her ESRD is due to pauci-immune vasculitis and has been treated with steroids and Cellcept. Work up for other causes of secondary pulmonary HTN is negative.
Would you do anything for secondary pulmonary hypertension (estimated PAP of 80-90 mmHG on echo) due to COPD before undergoing renal transplant? Her COPD is 2 to AAT deficiency and stable on AAT replacement. FEV1 of 40% predicted. She has documented nocturnal desat on sleep study without significant sleep apnea. But she is non-compliant with home O2. Daytime sat on RA is OK. She is not a smoker. She is on dialysis and her ESRD is due to pauci-immune vasculitis and has been treated with steroids and Cellcept. Work up for other causes of secondary pulmonary HTN is negative.
Monday, August 28, 2006
Alpha-1 AT
So, I saw a patient last week for Alpha-1 AT deficiency. Phenotypically, she has the disease--lower lobe emphysema, severe obstructive disease (FEV1 of 1.0 L which improved to 1.35 while on augmentation therapy with Prolastin). She has a family history of the disease and is a non-smoker (with substantial second-hand exposure). Her measured enzyme level, prior to the start of weekly Prolastin, was 31 mg/dl (lab range for normal is 100-190 mg/dl).
So, the interesting thing is that she (and her family members with the disease) has an M-Z genotype, which should be a "normal" phenotype without disease. The genotype was confirmed with separate studies, as was her son's genotype.
Anyone seen this before? Any comments?
So, the interesting thing is that she (and her family members with the disease) has an M-Z genotype, which should be a "normal" phenotype without disease. The genotype was confirmed with separate studies, as was her son's genotype.
Anyone seen this before? Any comments?
Wednesday, July 26, 2006
LVRS contra-indication
This question came up recently on this patient's follow-up. This is a relatively young man with HIV/AIDS who has done remarkably well on HAART (he had PCP 8 years ago!). He has the typical bullous emphysema associated with HIV and his previous smoking history. His emphysema is predominantly upper lobe (see below with a nice azygous "lobe"), he is hyperinflated and has air trapping. His FEV1 is still greater than 45% so LVRS is not for him yet anyway.
However, the question came up, is HIV infection an absolute contra-indication to LVRS?

However, the question came up, is HIV infection an absolute contra-indication to LVRS?

Thursday, July 20, 2006
AAT replacement
Question came in from here:
Just a quick question on alfa-1 antitrypsin replacement.
Do you use weekly regimen or monthly regimen? FDA has approved only once a week regimen. But I have read that monthly regimen is also "widely used in many centers." What is your experience on this? Monthly regimen would be off-label use. Has anybody experienced a severe adverse effect with monthly regimen?
Just a quick question on alfa-1 antitrypsin replacement.
Do you use weekly regimen or monthly regimen? FDA has approved only once a week regimen. But I have read that monthly regimen is also "widely used in many centers." What is your experience on this? Monthly regimen would be off-label use. Has anybody experienced a severe adverse effect with monthly regimen?
Wednesday, June 14, 2006
Alpha-1 AT augmentation therapy
One of my patients is a 55 y/o woman, heterozygous for A1AT with very low serum levels of A1AT (~65-75). Unfortunately she has continued to smoke and her FEV1 is 30% of her predicted with hyperinflation and decreased DLCO. She asked about "re-checking" her serum levels and whether she would be a good candidate for augmentation therapy. I have been less than excited with the ongoing smoking and pretty advanced COPD. I would be more interested in evaluation for a possible lung Txp in the future if she ever quit smoking. Her most recent serum level was 72. Would you consider A1AT replacement?
Tuesday, May 30, 2006
COPD and air travel
This was submitted by one of our readers:
My mother has bullous emphysema. i want to know how safe it is for her to fly commercial from tennessee to australia where i live for a visit. she was recently told that she might not be able to fly by a nurse. are there any special precautions she can take or things to do in this circumstance? I would really like to get her here for an extended visit if possible as she has not seen her youngest grandson yet.
My mother has bullous emphysema. i want to know how safe it is for her to fly commercial from tennessee to australia where i live for a visit. she was recently told that she might not be able to fly by a nurse. are there any special precautions she can take or things to do in this circumstance? I would really like to get her here for an extended visit if possible as she has not seen her youngest grandson yet.
Thursday, March 23, 2006
LVRS
Steve G. asks about lung volume reduction requirements. In a patient with heterogeneous emphysema in the upper lobes, what defines poor exercise tolerance? Is an exercise study necessary or can we use the 6 minute walk to evaluate? If so, how many meters would be considered poor?
Friday, March 10, 2006

Tuesday, February 28, 2006
Tiotropium and Ipratropium
When Spiriva was released, the official statement was that Ipratropium might compete with Tiotropium and, being less potent, decrease its benefit. The trials were done comparing the two but no add-on effect was measured. The PI actually states: "However, the co-administration of SPIRIVA with other anticholinergic-containing drugs (e.g., ipratropium) has not been studied and is therefore not recommended."
Our pharmacy interpreted that all Pts started on Spiriva should have Atrovent discontinued and Combivent switched to albuterol. How have you handled this?
Our pharmacy interpreted that all Pts started on Spiriva should have Atrovent discontinued and Combivent switched to albuterol. How have you handled this?
Wednesday, February 22, 2006
COPD and CxR below

The CxR did not project the RUL lucency as well as I hoped... Jennings pointed out some of the density increase in the left: he does have some scarring throughout but the left side looks denser because of the right lucency. Check out his CT scan.
What would you recommend.
Answer below in the discussion.
Tuesday, February 21, 2006
COPD and CxR eval.
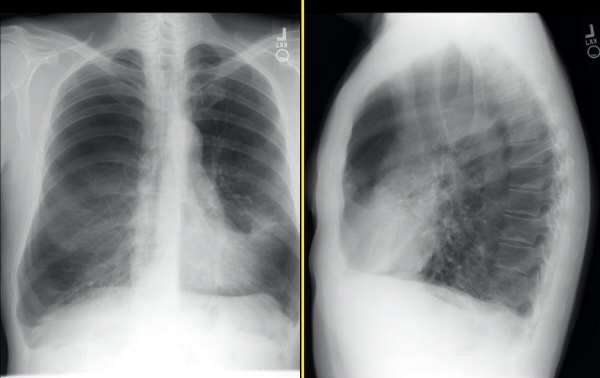
Hopefully this CxR will project fairly clearly. This is a 70 y/o man who finally quit smoking and has significant DOE. His PFTs on bronchodilators show some hyperinflation, very reduced DLCO and FVC~60% with FEV~33%. What do you think of his CxR?
Tuesday, February 14, 2006
When to treat Alpha-1 Antitrypsin
38 yo female with no PMH except A1AT deficiency diagnosed in her 20's when she was being worked up for abnormal liver tests. Her level then was 21 mg/dL (normal > 80). PiZZ phenotype.
Her PFT's (spiro only) in 1989 were completely normal per a dicatated report by a pulmonologist practicing at a now-closed hospital. The pulm specialist is now retired.
She was not treated with enzyme replacement.
She was referred to me after her PCP rechecked the level and again confirmed 21 mg/dL.
She feels well, exercises 5 days per week without any dyspnea. She has not had a resp infection since she was in her teens (when she smoked for about 5 years...1/2 ppd). She has no limitations.
PE: Normal.
Labs: AST and ALT in 50's. O/w normal (except A1AT level).
HER PFT's:
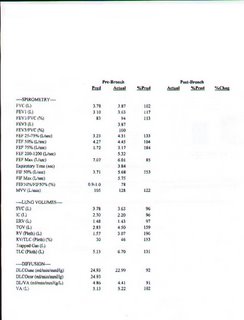
Would you treat?
If not, how would you follow and what would push you to treat?
Would you offer inhalers to this asymptomatic patient?
Her PFT's (spiro only) in 1989 were completely normal per a dicatated report by a pulmonologist practicing at a now-closed hospital. The pulm specialist is now retired.
She was not treated with enzyme replacement.
She was referred to me after her PCP rechecked the level and again confirmed 21 mg/dL.
She feels well, exercises 5 days per week without any dyspnea. She has not had a resp infection since she was in her teens (when she smoked for about 5 years...1/2 ppd). She has no limitations.
PE: Normal.
Labs: AST and ALT in 50's. O/w normal (except A1AT level).
HER PFT's:

Would you treat?
If not, how would you follow and what would push you to treat?
Would you offer inhalers to this asymptomatic patient?
Subscribe to:
Posts (Atom)