Wednesday, October 11, 2006

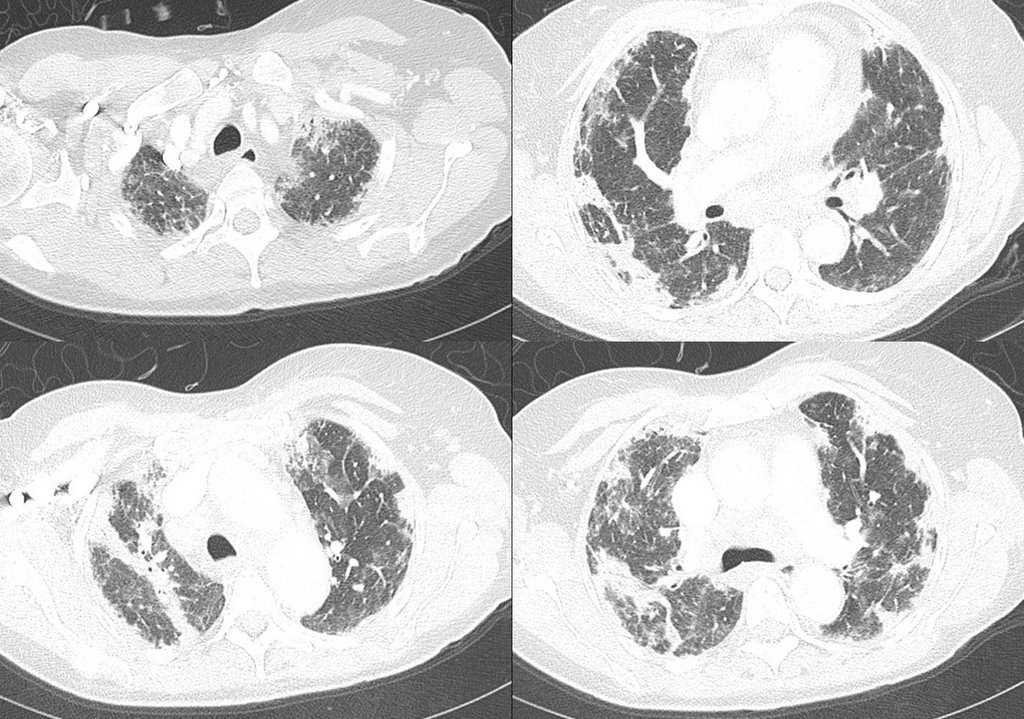
What is wrong with this picture?


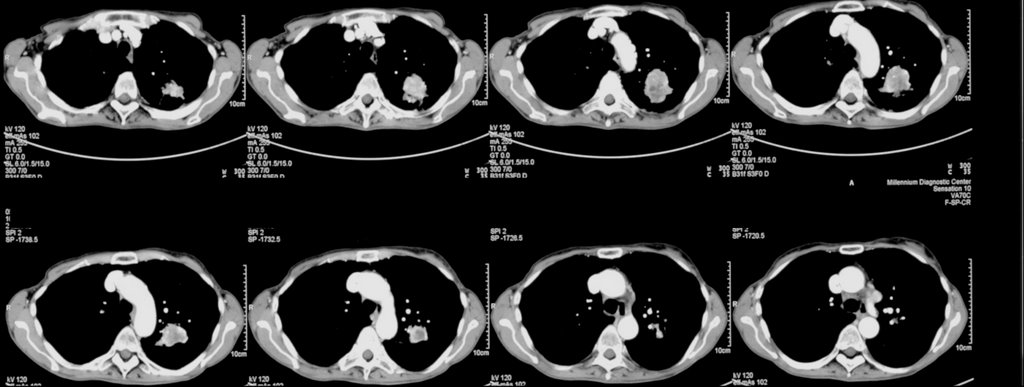
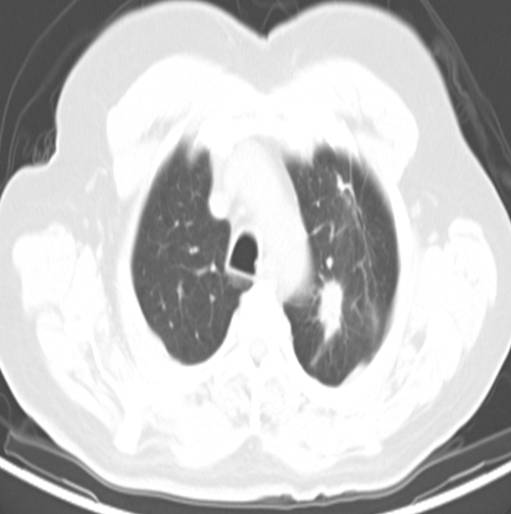
This 26 y/o man with a history of smoking 1 ppd cae to the ER with cough and new hemoptysis.

Tuesday, October 10, 2006

Persistent pleural effusion

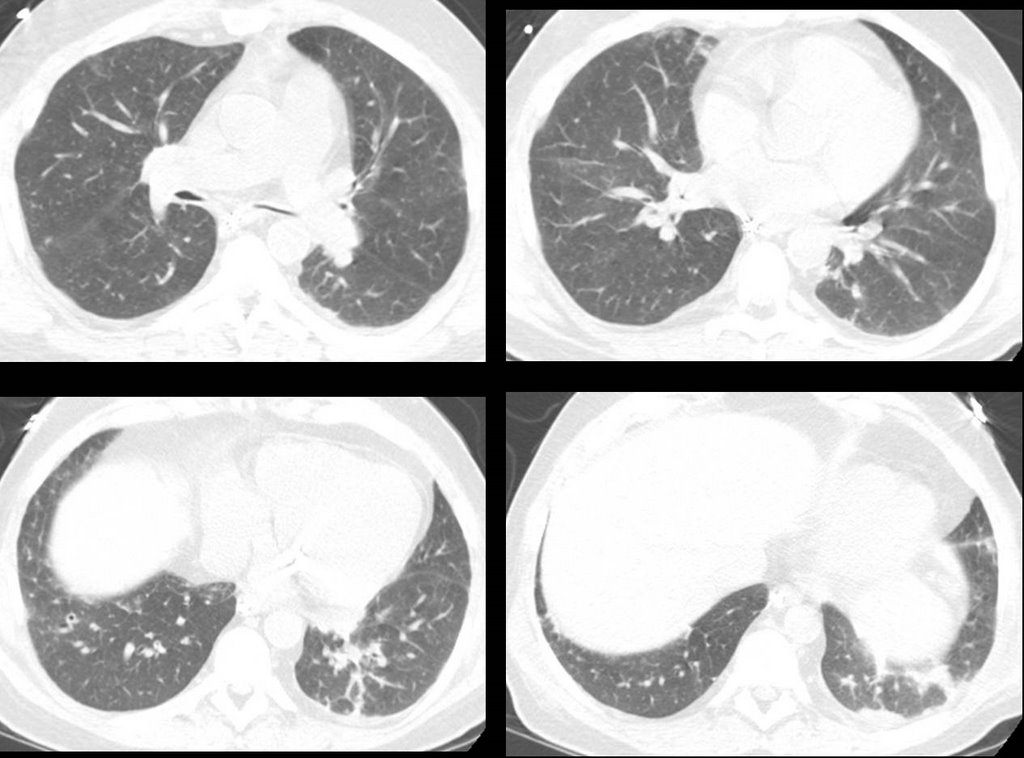
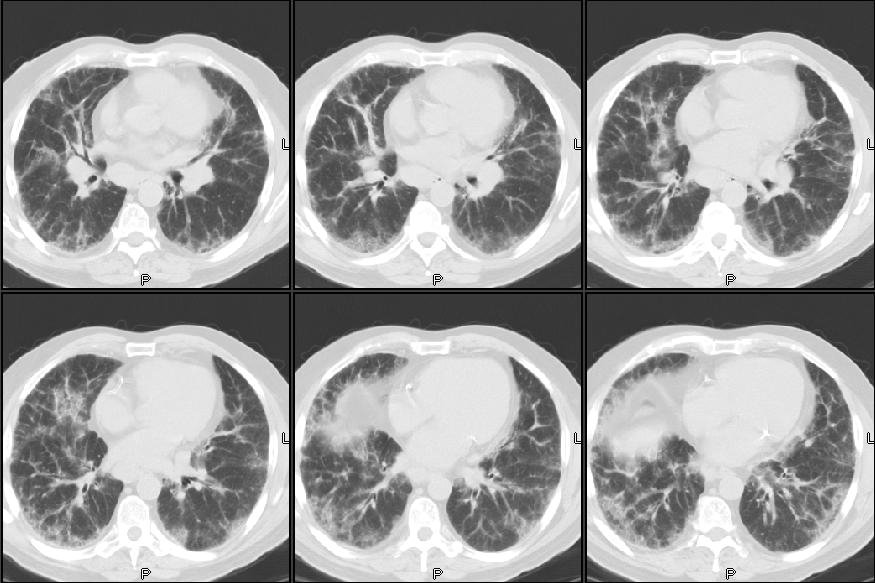
This is a 38 year old man who is 1.5 years s/p a bone marrow transplant for non-Hodgekin's Lymphoma that had relapsed despite several chemotherapeutic regimens. His post-transplant course has been generally uneventful, with good engraftment, no major infectious complications, and minimal GVHD of the skin and gut. He also had a DVT at some point, treated with adequate anticoagulation for 9 months. He was referred for a right pleural effusion. This was tapped-it was a chylothorax. Flow-cytometry was negative for a recurrence of the lymphoma.

His pulmonary function varies a bit between normal and a mild obstructive ventilatory defect. His exercise capacity has continued to improve since the BMT, but remains significantly below his pre-morbid state (he was, prior to his cancer, a highly trained endurance athlete).

He is referred for pleuradesis.

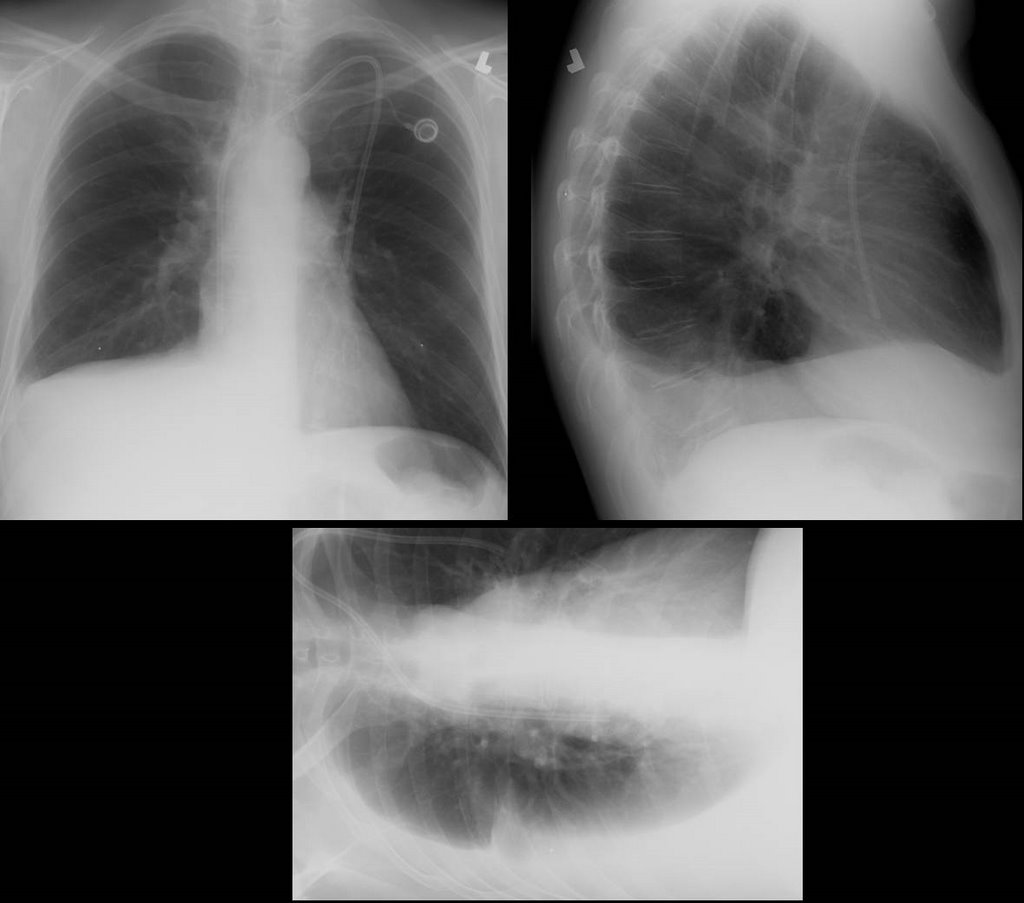
His films are below:

His pre-BMT film:


One year later, prior to thoracentesis:


One-day following a 2-liter thoracentesis


Thoughts? How would you proceed?

Monday, October 09, 2006

Change in mental status

45 year old man, presented with a persistant cough that did not go away despite 4 different antibiotic course, some kenalog, some anti-allergy meds, and finally a CXR that showed "Right middle lobe pneumonia"

He was admitted for the persistent cough.
ROS no weight loss, SOB, nightsweats. Just the cough (non productive).
SOCIAL HISTORY: married,self-employed painter. He smokes cigars usually five times a week. He averages six to 12 alcohol beverages per week.

On exam the next day he was alert but confused. His vitals were normal as was his saturation on room air. He did not answer questions. He just looked at his wife and smiled. A Na was 129 when before on admission it was 137. The rest of the labs were unremarkable. LP, EEG and head CT were done but negative. By the trime some of that came back he was already becoming more oriented on his own. The next day he was a/o x 3.
Any feedback before I proceed?

Wednesday, October 04, 2006

Dyspnea and a LUL mass

Here's a case from Arenberg:

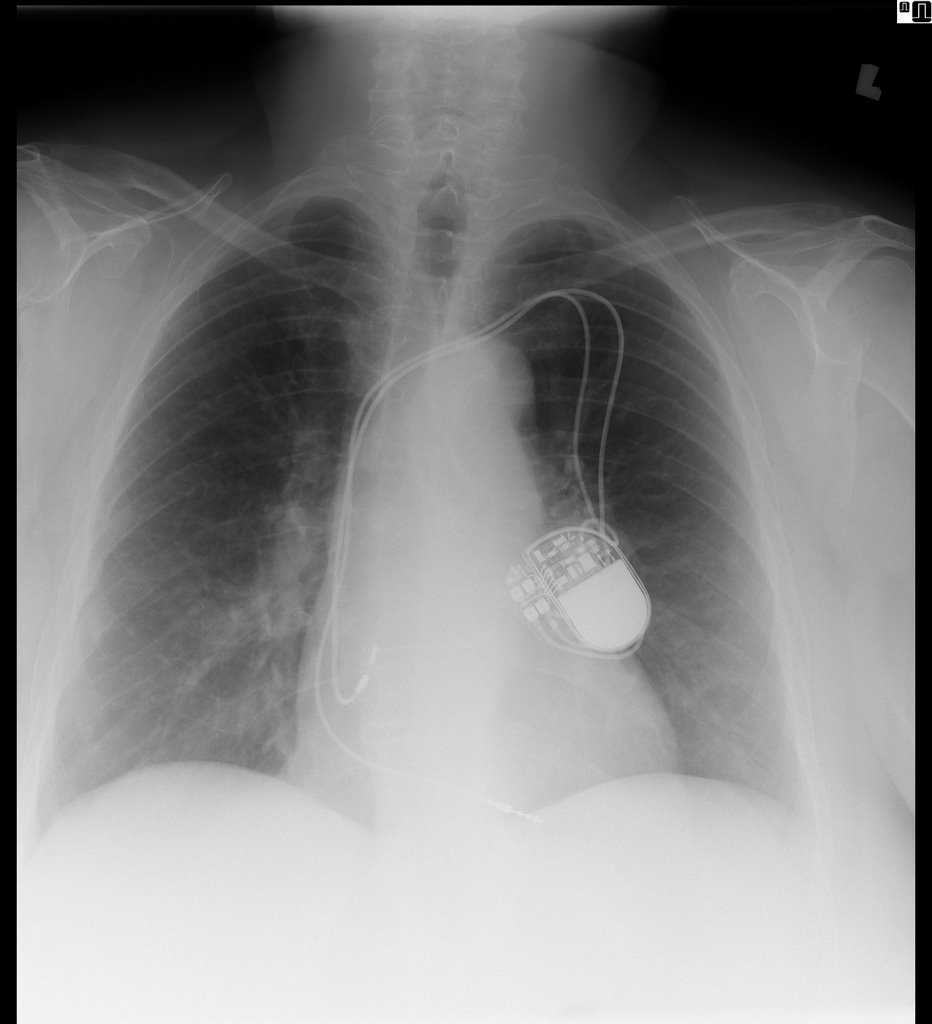
This is 69-year-old lady with coronary artery disease, diastolic congestive heart failure, and dyspnea on exertion. She came to see me because her cardiologist said she has been experiencing increased dyspnea out of proportion to her normal symptoms for ~3 months. Other than a pacemaker over her left chest, her plain chest x-rays were normal

and her pulmonary function tests were mildly restrictive (FVC ~69%), actually improved from her last testing ~ 4 years prior.

I got a VQ scan that was normal, but only on her second visit (when I actually asked) did I learn that she has had 2 birds as house pets for the last 3 years. She further revealed that she has felt unwell going back about 2-1/2 years. One of the birds was in fact sick, and during this time, she fed the bird from mouth to mouth. Yes, I am serious. She was DEAD SET against getting rid of the birds, so I got a CT scan in anticipation of doing a bronch, to prove she had HP.

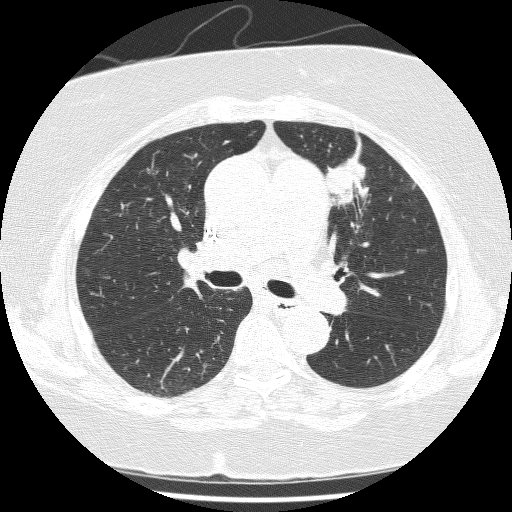
The CT showed very subtle changes of ground glass, and was actually read as no evidence of ILD, but surprise surprise, she now had a LUL mass that was not seen on the CXR taken 2 months earlier. The radiologist thought it was likely to be inflammatory. What would you do?

I have more images, and some cool pictures to follow, but I’ll hold onto them until people have a chance to comment.


--------------------------
UPDATE:
"...good evidence for chronic HP in the form of a patchy chronic
bronchiolitis that includes occasional multinucleated giant cells of the
sort commonly seen in that condition"

Comments from our pathologist.

Tuesday, October 03, 2006

Varenicline

Have you had the chance to start patients on Chantix yet?
What has your experience with it been thus far? Any good success stories?

Friday, September 29, 2006

Sepsis and steroids

IS:
This is not a case presentation, but want to take a poll on what people are doing about steroids and sepsis. Do you administer steroids emperically after initial fluid bolus or do you attempt resuscitation per the 6hr bundle first and then administer steroids if still on pressors or hypotensive?

Tuesday, September 26, 2006

Follow-up to Anti-GM-CSF

I had posted this question but had no takers so I am posting a suggested answer. The Cleveland Clinic has an (investigational) Anti-GM-CSF autoantibody kit available for primary PAP. Check out this link for more info.

fluid filled lesion

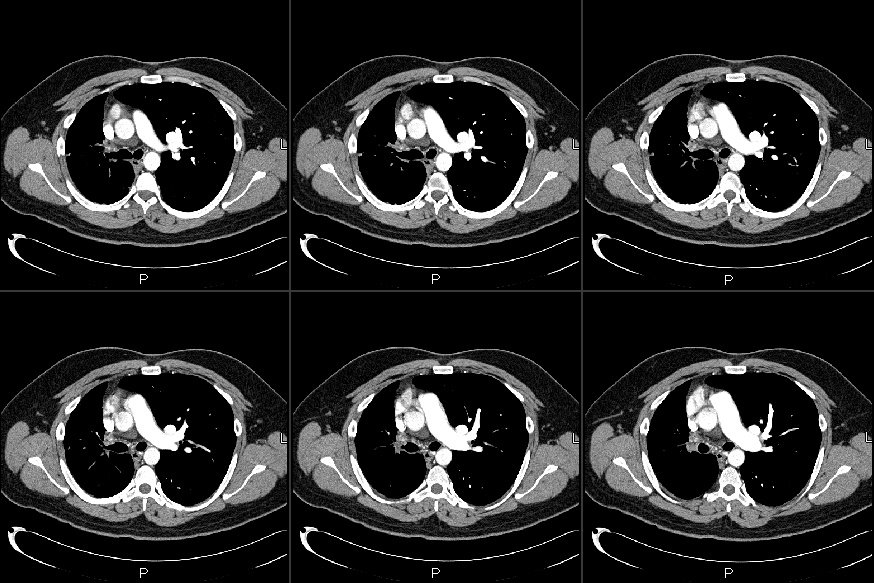
"Anonymous" sent us the following CT slices of a 38 year old who presented with cough and fever. AFB were negative x 3. He was not very productive of sputum and what they did get had many epithelial cells.
How would you proceed if this was your patient?

Update on Mass and Infiltrates

I had posted on this 59 y/o woman with a funny presentation: she had had an episode of syncope at home, hit her head and had a skin lac requiring 7 stitches. While being worked up in the ER they found her to be hypotensive and febrile with an abnormal CxR and CT of the chest. She had MSSA in her sputum and a dense lung "mass". I bronch'ed her and got "organizing pneumonia" but no malignancy. She got ABTx and the "mass" went away completely. She did however had persistent smallish alveolar infiltrates seen below:

I re-bronched her focusing on the infiltrates since they had persisted for 3 months after the initial presentation. She had a lot of eosinophilic proteinaceous alveolar material and our pathologists sent the tissue to T. Colby who thought this was PAP.
Would you be satisfied with this Dx on TBBx or would you pursue an OLBx?
How about testing for anti-GM-CSF Antibodies?
She has almost normal lung function, how would you treat her?

Hemodynamics

A patient intubated and sedated for hypoxia (history of aspiration although CXR negative) had initial swan numbers of: CO 5 L, CI 3.24 PAP 26/16. PCW 8 with cvp of 4. SVR 1362. PVR is 190. AFter fluid boluses with no change in CO, PCW still 8 with a CVP of 6. His SBP has been 116/78 basically unchanged throughout. After fluid blouses he is now about 10 L up with really no change in the above swan readings or bloodpressure. How would you interpret this? Of note a surface echo showed an EF of 25-35%.

Here's his cxr.

Thursday, September 21, 2006

Anti-GM-CSF antibodies

Have you been checkin anti-GM-CSF antibodies for evaluation of suspected PAP? If so, is there a commercially available ELISA or have you been sending those to the Cleveland Clinic?

Monday, September 18, 2006

Follow-up to Pulmonary-thyroid

This is the patient with the hot pulmonary nodule and lung mass.
We decided to start with the thyroid and a bronch. The thyroid mass (it was not cystic on CT) was a follicular carcinoma with local invasion. No lymphnodes and the other lobe was clean.
The bronch was non-diagnostic and radiology felt the mass was too low and there was too much lung in its way for a good CT-guided needle.
She went to see our CT surgeons and we figured out why the bronch was non-diagnostic: it was not a lung mass but a diaphragmatic mass. It was an aneuploid adenomatoid tumor still not clearly characterized. Incidentally, there was a second focus of this same adenomatoid tumor in the superior segment of that LLL, which had not been seen on CT or PET (at ~7mm).
What do you think?

Friday, September 15, 2006

Radiology Friday

This patient has a pleural effusion. Which fissure (and which side) is this?

Wednesday, September 13, 2006

The pulmonary-thyroid connection


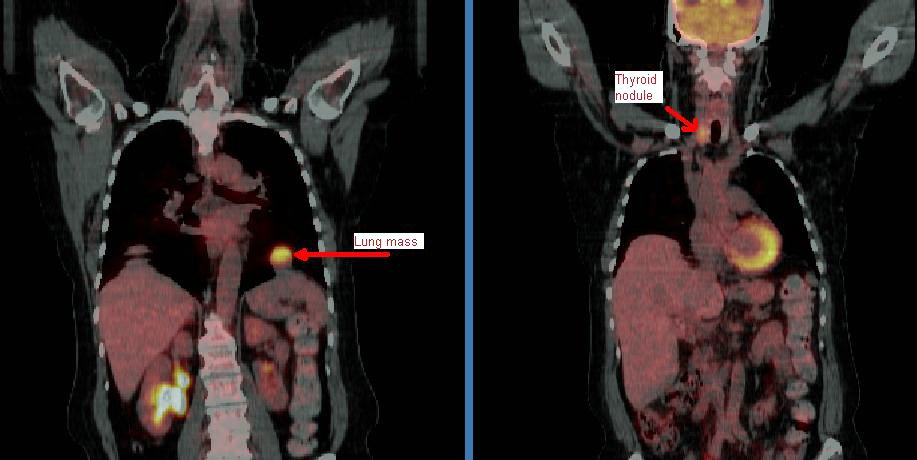
This patient came to me pre-worked up so I will show all the data she had had thus far. This is a 65 y/o woman with no TOB Hx, normal PFTs who had a persistent cough. She had an abnormal CxR (see above) and here PCP ordered a CT and then a PET-CT and she was sent to us.
Her PET scan showed two very FDG-avid lesions. A L basilar lung lesion and a R thyroid nodule with no other abnormal uptake. She is euthyroid clinically and by TFTs.
Do you think the lesion are related?
Would you biopsy one, the other, both?

Tuesday, September 12, 2006

LUL lesion, still undiagnosed

70 year old woman with COPD FEV1 34% predicted, but she is well compensated and on no supplemental oxygen (91% on RA). A LUL lesion was noted (see below) and workup included 2 bronchs (one with ultrasound-guided) and 1 CT-guided biopsy. All were negative for malignant cells. BAL was not done but Tbbx showed Atypical lymphoid cell with acute inflammation and Filamentous bacteria. BAL was not sent so we don't have micro ID (the bacteria was identified by path).


Cancer is obviously still number one on the list, but I dont think she's a surgical candidate and in terms of treating with chemo, we still dont have a tissue diagnosis. On the other hand, the filamentous bacteria finding is interesting. What is your impression and what would you all do next? Thanks.

Monday, September 11, 2006

Bloody effusion

57 y/o man former smoker, presented with pleuritic CP and found to have left loculated effusion. No constitutional sx. no wt loss, fever, chills, cough. Tap 2 weeks later showed it to be bloody, with 57 WBC, 49% PMN and 49% lymphocytes. He is currently asymptomatic.

The effusion was AFB - times 1. The micro and cytology was negatrive. Dopplers of legs negative and V/Q was intermediate or indeterminate (cant remember) and PE-protocol CT was read as negative.

His Pmhx not remarkable except for 2 previous pneumonias. Last was in march and was on the right side. There was a small parapneumonic effusion which has since resolved.

No history of trauma except moving his furniture 1 day before the pleuritic CP, but he did not hit anything per se. No Fmhx of thrmbosis and in fact his Wells criteria is zero.

What would you all do next?

Thursday, September 07, 2006

Advice on further workup for this lung cancer.

59 year old ex-smoker with FEV1 1.17 liters (47% predicted) who has a left upper lobe lesion:


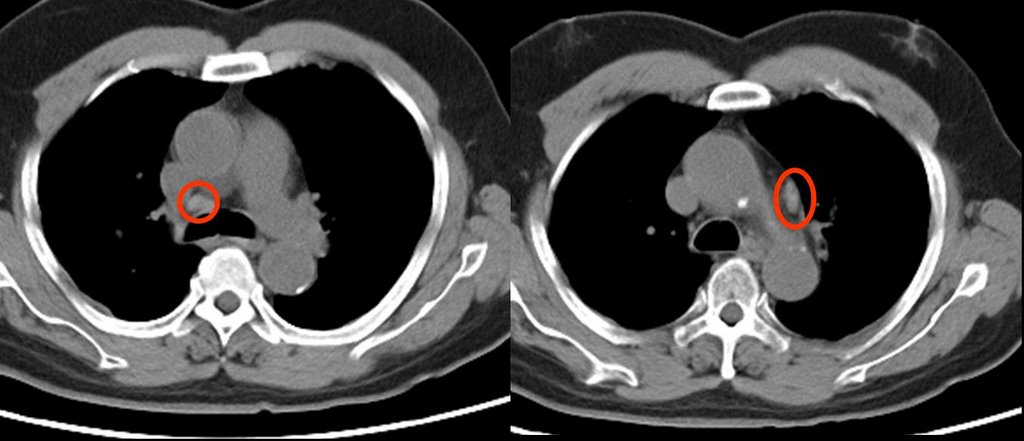
He also has some enlarged nodes (red circles):


The PET showed intense uptake of the LUL lesion and "mild hypermetabolic activity in the right hilar and pericarinal regions corresponding to nonenlarged lymph nodes on CT. This is of uncertain clinical significance. No other foci of abnormal hypermetabolic activity are identified.":


However, because of the enlarged nodes and the equivocal uptake on PET , I elected to sample them anyway;
The results showed no malignancy from the fine needle aspirate (but there were lymphocytes indicating that the node was sampled.
Not surprisingly, biopsy of the peripheral lesion in the LUL lesion was indeed cancer - adenocarcinoma.


Would you call this cancer a stage I (tumor was 2.4 x 1.4 cm) and proceed to surgery?

Wednesday, September 06, 2006

Multiple pulmonary nodules

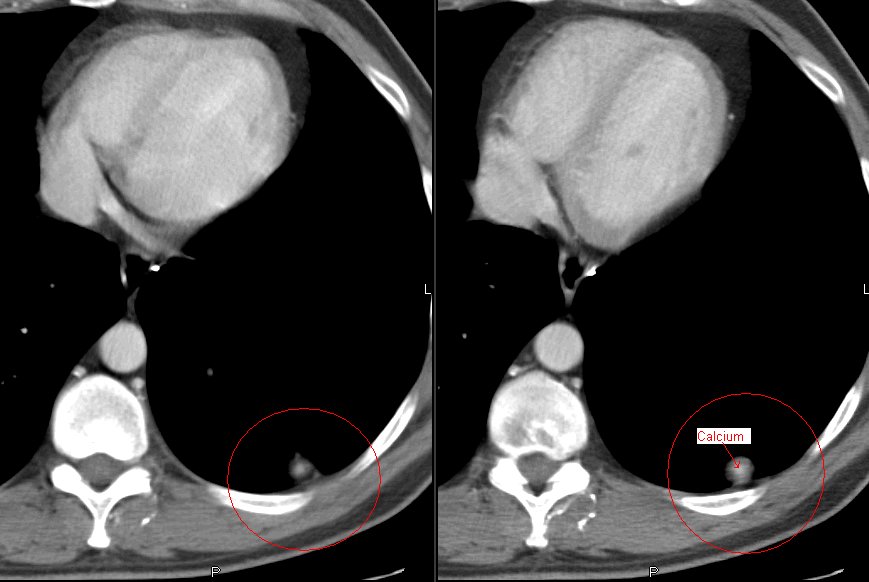
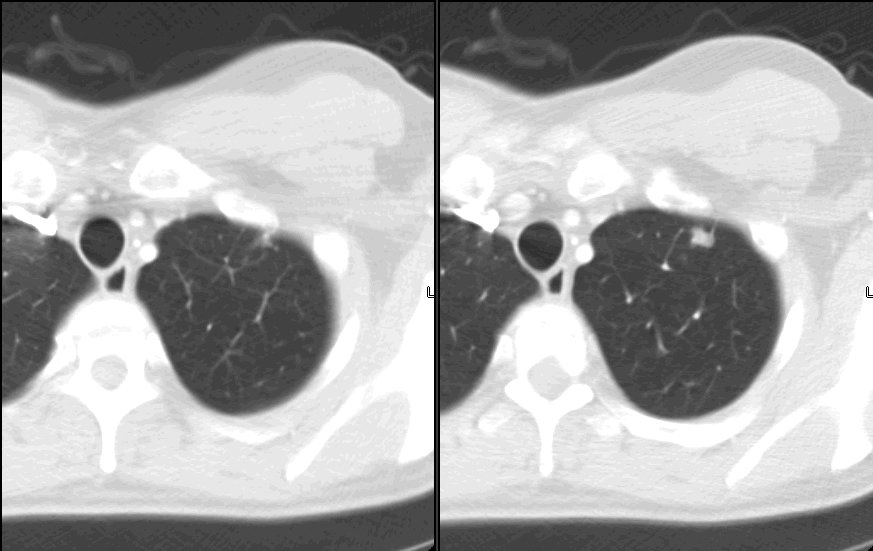
The patient is a 69-year-old African-American woman who came to pulmonary clinic for multiple pulmonary nodules that were picked up in the course of abdominal CT for workup for abdominal pain with increased LFTs (which have since normalized). She has a history of hypertension, diabetes, peripheral vascular disease, and hyperlipidemia. She is a nonsmoker. No fever chills cough SOB, diaphoresis or constitutional symptoms.
Exam: A pleasant woman in no acute distress. WT of 197, BP 185/83, P is 65, R 18, O2 sat is 97% on room air. Trachea midline. No lymphadenopathy and no supraclavicular adenopathy. No thyromegaly. Lungs: Clear to auscultation. No wheezing, rales, or rhonchi. No dullness to percussion. No egophony, symmetric chest wall on inspiration. Heart: Regular rate. S1, S2. Abdomen: Positive bowel sounds. No masses. No liver edge felt. No clubbing, cyanosis, or edema.

Data:
PFT's: FEV1/FVC 81, FEV1 76% predicted, FVC 73% predicted.
CBC with hemoglobin of 10.3, MCV of 94.6. Plts normal. Lytes-7 normal. ANA and rheumatoid factor negative


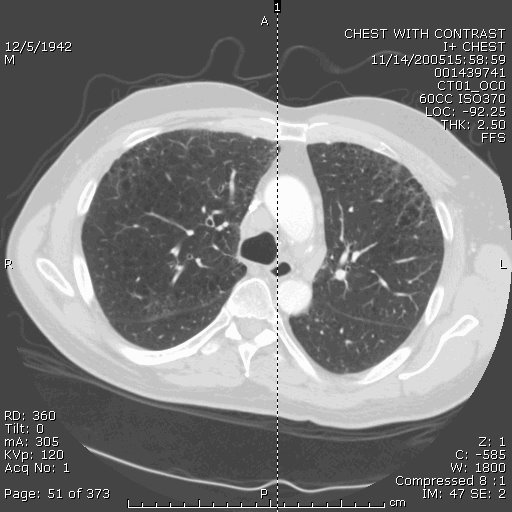
These nodules are all non-calcified. The largest is 8 mm. There is interval growth of left lower lobe nodule and right apical nodule compared to a CT 6 months prior. The subcarinal soft tissue is "prominent" but ambiguous whether it's enlarged.

On abd CT, the spleen, pancreas, kidney, gallbladder and adrenals are unremarkable.
2 calcified hepatic granulomas are seen.

Any thoughts on workup or management?


.

Tuesday, September 05, 2006

Pulmonologist with high IgE

At ATS there was a stand on a rapid IgE testing system on capillary blood and some of us had it done just to check out the system.
One of us (with Hx of rhinitis but noasthma) had the results come back at an IgE level of 900 (their upper limit was 136).
Would you investigate it any further (CBC with diff, etc.) ?

Thursday, August 31, 2006

Benign uterine fibroids and pleural effusion

This is an outside submission for a question correlating a pleural effusion and Gyn disease:
Patient with a right pleural effusion, more than 1500 ml tapped. 2nd tap: more than 1700 ml tapped 6 days later. Contrast CT revealed pelvic fibroids.
Effusion results protein, probably assoc. w/ RBC.5 to 11 months prior, sonograms, contrast MRI revealed uterine fibroids 8 to 10 mm in size, stable in size over 6 months. Uterine scrape (not complete D and C) test benign. No indications of ovarian cysts, etc. Hysterectomy not chosen due to stable fibroid size and results of uterine scrape.Heavy coughing for 9 mos. Chronic post-nasal drip for 23 mos.
Allergy tests reveal slight allergy to a few local plants.
Chest xray showed: Pleural effusion right side.
Latest contrast CT pelvic fibroid.Previous ultrasound and contract MRI showed uterine fibroids stable after approx 6 mos.
Effusion samples from 2 taps have no cytology assoc. w/cancer, no pancreatitis, tb/fungus results not yet available. Unremarkable except for protein.
2D echo unremarkable.
Any suggestions on this reaccumulating effusion?

Wednesday, August 30, 2006

Diagnosis and staging of lung cancer

Anonymous asks, If a patient, on chest CT, has a mass invading the hilum and mediastinum and there is also a pleural effusion, would you be able to simply do a thoracentesis for cytology and forego the bronch?

My take is that a bronchoscopy would not be neccessary, as a positive effusion will both diagnose and stage it as a T4. What do you think?

Monday, August 28, 2006

35 year old with cough, chills

35 year old without PMhx except a MVA 5 years ago, anxiety and depression. Now with chills and subjective fever and weight loss for the past few months. Meds: Paxil. Fhx: brother died of liver failure, patient does not know etiology. SH denies IVDA. 2 PPD x 20 years. Quit 5 yrs ago. HIV negative. Exam Afebrile. VSS. Some decr breath sounds upper lung zones b/l. WBC 11.


What would you do next?

Alpha-1 AT

So, I saw a patient last week for Alpha-1 AT deficiency. Phenotypically, she has the disease--lower lobe emphysema, severe obstructive disease (FEV1 of 1.0 L which improved to 1.35 while on augmentation therapy with Prolastin). She has a family history of the disease and is a non-smoker (with substantial second-hand exposure). Her measured enzyme level, prior to the start of weekly Prolastin, was 31 mg/dl (lab range for normal is 100-190 mg/dl).

So, the interesting thing is that she (and her family members with the disease) has an M-Z genotype, which should be a "normal" phenotype without disease. The genotype was confirmed with separate studies, as was her son's genotype.

Anyone seen this before? Any comments?

Thursday, August 24, 2006

Prune-belly

I have just seen a 26 y/o patient in the office for recurrent respiratory tract infections. He has a Hx of prune-belly syndrome (poor abdominal muscle development with severe urinary tract abnormalities) and has been on HD after a failed renal Txp.
These patients tend to have a restrictive physiology because of the oligohydramnios and sometimes even have hypoplastic lung. Indeed his TLC is ~66%. His Cxr is pretty unremarkable but he also has an associated obstructive defect: FEV1 is ~36% witha ratio of<70%. Has anybody seen this condition (or similar ones) be associated with asthma/reactive airways disease?

Tuesday, August 22, 2006

CPET

What do you think of this CPET data?
61 y/o obese woman (BMI: 37.3), S/P remote CABG with patent grafts and normal LVEF on recent angiography with persistent DOE. Very remote smoking Hx with only a mild restrictive defect (FVC~70% with FEV1/FVC>80), normal DLCO and normal HRCT. Negative methacholine challenge.
DATA (predicted values and/or percentages):
VO2max (ml/kg/min): 14.4 (25.4/56%)
AT: 0.749 (>0.698) - 43% predicted VO2max (>40%)
Max HR 73% predicted with still good reserve: 44. O2 pulse 11.5 (8.4)
VE max: 50.7 (65.9 / 77%)
Vt: 1.28 (0.563)
Respiratory rate: 36 (<50)
Breathing reserve: 2% (20-40%)
Vd/Vt at rest: 0.51 (0.30)
Vd/Vt at peak: 0.26 (0.18)
RQ: 0.93 (1.1-1.3)
No desat.
FVC at peak declined by 19% and FEV1 at peak did not change.

Monday, August 21, 2006

Anemia

This is more of a critical care than pulmonary question. It came up today in discussion with renal...
The gold satndard for iron-def. anemia has been staining the bone marrow for iron stores. Nobody does that much anymore as first test since ferritin has such a good correlation with iron stores. The discussion was whether you can have iron-deficiency anemia with good normal ferritin (not normal-low, low-normal, borderline, etc.). Even though ferritin is an acute phase reactant and may mak a borderline ferritin level seem normal it shouldn't push it to the mid-high range. (ferritin will roughly triple as an acute phase marker, Ann Rheum Dis 1986 Jul;45(7):596-602)
Do you look at the iron/iron sat or do you trust the ferritin?

Thursday, August 17, 2006

Failure to wean

This is a 44 year old man with DM, s/p renal transplant several years ago. He has the other associated micro- and macro- vascular problems associated with DM, including severe PVOD and a non-healing, chronic LE cellulitis for which a BKA has been recommended (but refused--he is on chronic supressive antibiotics). His immunosupression includes cyclosporine and prednisone.

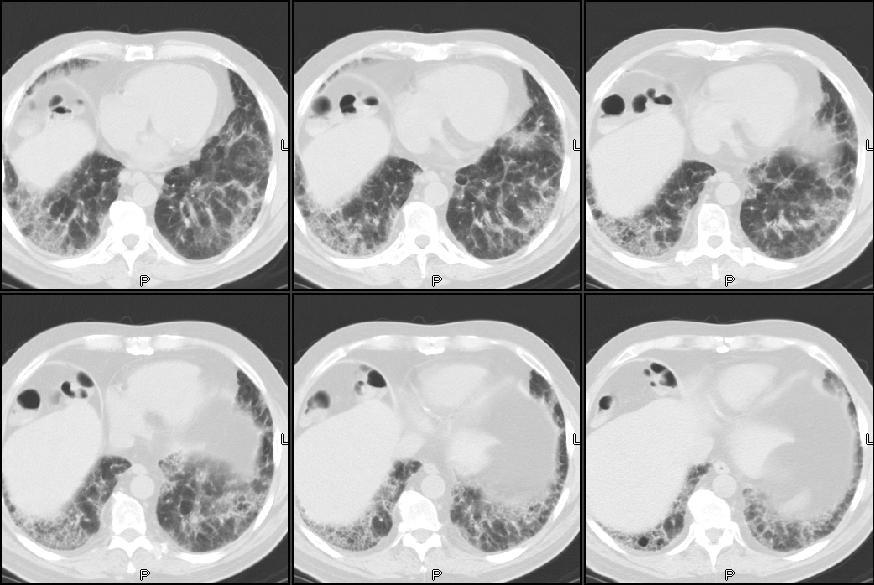
He was admitted to the ICU with hypoxemic respiratory failure requiring intubation for what turned out to be herpes pneumonitis, and was treated with a 21 day course of acyclovir. Over this course, he was easily ventilated and oxygenated with progressively improving respiratory parameters. On two occasions, his weaning parameters were excellent, and he easily tolerated minimal ventilatory support (PS-5/PEEP 5) for 2 hours. Each time, he required re-intubation for respiratory distress several hours after extubation.

Here's some representative cuts from a CT scan done about 10 days into his hospital course.


Tuesday, August 15, 2006

PET and staging

I saw this patient in follow-up today.
This is an 82 y/o woman with no smoking history but decades of second-hand smoke (her husband died of lung dz). She had a dry cough and a CT scan was done. She has the large LUL mass seen on the CT cut (on an outside CT with contrast, the mass seems to invade the PA). I did a bronch and the mass is a non-small cell Ca. Unfortunately, the hilar TBNA were non-diagnostic. Her PET scan shows marked uptake by the mas, ipsi- and contralateral hilar nodes and pre-tracheal nodes.
With the PA involvement (on CT) and the PET results would you be satisfied in calling it a IIIB or would you do a mediastinoscopy to confirm either/both with tissue?

Monday, August 14, 2006

Outside case: Adenopathy

This was submitted to us:
34yr.old female w/ previous rt low lobe nodules since 2001 CT revealed the nodules while patient had chickenpox.
New CT in 2006 shows new node on lt. upper diaphragm. Last CT 6mo. prior didnt show nodule, which is uncalcified unlike rt. lung nodes.
PT. has nightsweats wt. loss chronic pelvic abdominal pain jointpain/swell/stiff no appetite ab.bloat chronic urinary symptoms and UTI.
Now with SWOLLENLYMPHNODES W/LYMPH SURFACING AND RUPTURE ON NECK BACK OF HEAD BEHIND EAR. PT. is 11/2 ppd smoker of 13yrs. PET done 4/06 and no malignant chest activity. labs almost normal.

Wedding bells

Congratulations to one of our editors: Jeff Jennings tied the knot this past weekend.
We will keep posting while he is on his honeymoon.

Wednesday, August 09, 2006

Acid Base

The chem-7 and the gas were both drawn within 22 minutes of each other in this 71 year old intubated man with sepsis and ARDS:

7.08/24/226 on fio2 of 75%

Na 145
k 5.2
Cl- 114
HCO3 28
BUN 42
Cr 0.5

What is the acid base disturbance?

Proceed or watch? Is it CA?

Here is a case submitted to us:

8/1/06 49 YO Caucasion male, married with minor children, comfortably employed professional, USAF Gulf War Veteran, 2-3 PPD smoker X30 years, ETOH dependent (averages 6-10 beers daily)presents with R clavicular pain after home remodeling project. Well developed, well nourished, muscular, athletic body type. VS WNL. Non remarkable EKG. Clavicle XR demonstrates shoulder separation with incidental 1.75cm diameter spiculated nodule mid upper right lobe lung, mild emphysematous changes. CT confirms nodule. PET eyes to knees results no demonstrative uptakes. CBC, Metabolic panels normal. CEA and CA125 WNL. PFTs near normal, demonstrates ability to tolerate surgery.

Family HX: Maternal died d/t +NSCL CA with brain, liver mets. Paternal +adenocarcinoma colon, in remission post colectomy and chemo. No other significant family HX or disease.

Smoking Cessation in process with nicotine patch use. ETOH use diminishing. Pt. wants no invasive surgery or BX unless absolutely indicated. Lesion is not near bronch, no bronchoscopy in plan. What next?

Tuesday, August 08, 2006

Mass and infiltrates

This is a 59 y/o woman with a funny presentation: she had an episode of syncope at home, hit her head and had a skin lac requiring 7 stitches. While being worked up in the ER they found her to be hypotensive and febrile with an abnormal CxR and CT of the chest. She had MSSA in her sputum and the dense "mass" seen on the left images. I bronch'ed her and got "organizing pneumonia" but no malignancy. She got ABTx and the "mass" went away completely.
She has felt better and has good PFTs. However, it has now been 3 months and the peripheral faint patchy areas of reticular disease remain there and unchanged.
She has only minimal DOE. She quit smoking in 1988 and has no unusual exposures.
How would you pursue this little infiltrates? (they are present in the lower lobes as well).

Thursday, August 03, 2006

Halleliujah

From Arenberg:
"In celebration of the fact that the IT people in the Department of Radiology at the University of of Michigan have recognozed that their department exists to provide films for other doctors to look at, and have finally made it into the 21st centry by providing consistent, relaible online access to films for the unwashed masses (read: non-radiologists)...I hereby submit this film of an unfortunate man with a history of cancer."

Monday, July 31, 2006

Follow up to pleuritic pain and fatigue

Old case presented by Mendez is here.

Follow up: Transbronchial bx's revealed multiple epithelioid granulomas. Special stains for AFB and fungi were negative.


Symptoms improved after treatment with oral prednisone which was tapered over several months.

F/U Chest CT (6 months later) revealed interval regression of peribronchovascular nodularity. Previously enlarged hilar/mediastinal lymph nodes no longer enlarged.

Final Dx: Stage II Sarcoid

Sunday, July 30, 2006

Pulmonary nodules

This is a 44 y/o man who works here in the hospital. He is a ctually a nice guy so I'm trying not to find anything too interesting on his case.
He is very healthy and smoked a pack-a-day for ten years but quit in 1988. He had travelled to the gul area and came back with a severe gastroenteritis. It seems that it was so bad the primary team got a CT of his abdomen. He did OK but the lower cuts of the lung revealed a ~1-cm partially calcified LLL nodule. He is completely asymptomatic from a respiratory perspective. His PFTs are completely normal. We got a dedicated CT of the chest and found the following nodules: (a 9-mm RUL a ~5-mm L apical and the same LLL).
The RUL has a little bit of excentric calcium as does the LLL one. Would you PET, biopsy, watch or else?

Thursday, July 27, 2006

mediastinal nodes

Case submitted from outside:

63 year old smoker with hypoxia. CXR looks extremely hyperinflated. PFTs with ratio of 0.67, FEV1 87% predicted and FVC 93%. Lung volumes normal except for an inspiratory capacity of 73% predicted (volume done by helium dilution). DLCO 35% predicted. CT scans included below and are basically unchanged from 7 months ago. Mild mediastinal LAD, with the largest being approx 2cm. Also stable over 7 months. Would anyone pursue a biopsy of the nodes or the lung? Other thoughts?


Wednesday, July 26, 2006

LVRS contra-indication

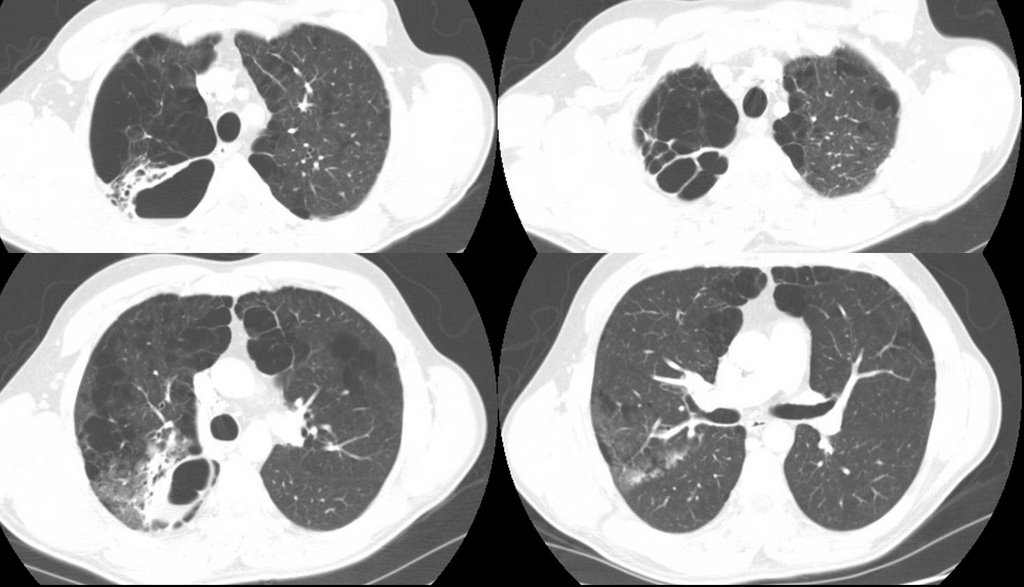
This question came up recently on this patient's follow-up. This is a relatively young man with HIV/AIDS who has done remarkably well on HAART (he had PCP 8 years ago!). He has the typical bullous emphysema associated with HIV and his previous smoking history. His emphysema is predominantly upper lobe (see below with a nice azygous "lobe"), he is hyperinflated and has air trapping. His FEV1 is still greater than 45% so LVRS is not for him yet anyway.
However, the question came up, is HIV infection an absolute contra-indication to LVRS?

Tuesday, July 25, 2006

New lung nodule

This is a 72 y/o man with a significant previous TOB Hx, moderate COPD who was referred to us for a new pulmonary nodule. He has had multiple urologic surgeries including a nephrectomy for transitional cell ca (it seems he had a "high" transitional ca of the calicial system). He has a new nodule on the contra-lateral (remaining) kidney and had a new CT and a pulmonary nodule was found. This is a LUL non-calcified nodule with no air-space disease and no thoracic adenopathy.
A bronch was non-diagnostic and a PET (see below) only showed intense uptake on the nodule and nowhere else (the remaining kidney had its usual physiologic uptake).
Do you think the two lesions are related? Would you try and FNA the lesion? His PFTs would tolerate a lobectomy. Would you just go straight to surgery?

Monday, July 24, 2006

More on the woman with eosinophilia

Well, as you might remember, this patient with a past medical history of asthma had had a few months of dyspnea and malaise. A peripheral showed 42% eosinophils and a BAL showed 20% eosinophils. A transbronchial biopsy showed eosinophilic infiltration. Micro was negative. Stool O&P was also negative.
She was given steroids with subjective improvement. However, I am not entirely satisfied with a diagnosis of chronic eosinophilic pneumonia. Here are her radiographs:


Now her amylase and lipase are elevated which does not go with eosinophilic pneumonia, and I don't have a good reason for that. Any thoughts out there? If it is parasitic, at least she is not worsening on the steroids....

Thursday, July 20, 2006

AAT replacement

Question came in from here:

Just a quick question on alfa-1 antitrypsin replacement.
Do you use weekly regimen or monthly regimen? FDA has approved only once a week regimen. But I have read that monthly regimen is also "widely used in many centers." What is your experience on this? Monthly regimen would be off-label use. Has anybody experienced a severe adverse effect with monthly regimen?

Radiation and lung cancer

I think it is my week to pick on radiation Tx... I already posted on the time delay notion (BTW, check out the PPT on that listed on the comments section).
What is your impression/practice on the use of xRt and lung cancer?
It certainly has an excellent role in symptom palliation, particularly with painful bony mets and other solitary mets presentations. It does decrease local recurrence (though it has less of an impact on survival) in locally advanced disease but it seems to me that it is automatically lumped with chemo as if you must have one with the other.
As a single modality (“curative xRt”) kind of falls short:
In a review of ten studies that utilized megavoltage irradiation to doses of >55 gray (Gy) in conventional fractionation for patients with medically inoperable Stage I lung carcinoma, only approximately 15% of patients were long term survivors (vs surgery and multimodality Tx). Cancer 1998 Feb 1;82(3):433-8
Similarly, five-year survival was only 19 percent in a series of "medically inoperable" patients with stage II disease. Radiat Oncol Invest 1996; 4:165
And the data on post-op xRt is not as good as post-op chemo:
In a French trial of post-op xRt vs. observation only, five-year overall survival was 43% for the control group and 30% for the radiotherapy group (P = 0.002). Cancer 1999 Jul 15;86(2):265-73
The older Lung Cancer Study Group from 86 showed no evidence that radiotherapy improved survival, and although recurrence rates appeared to be somewhat reduced among patients assigned to radiotherapy, these decreases were not statistically significant. N Engl J Med 1986 Nov 27;315(22):1377-81
In the IALT trial, which focused on post-op therapy and showed a benefit for chemo,
only 70.4 percent of those assigned to receive adjuvant thoracic radiotherapy in the chemotherapy group actually received xRt and the control group had actually a higher rate of xRt. N Engl J Med 2004 Jan 22;350(4):351-60
The PORT meta-analysis even showed a significant adverse effect of postoperative radiotherapy on survival (hazard ratio 1.21 [95% CI 1.08-1.34]). Lancet. 1998 Jul 25;352(9124):257-63
Even in stage III dz, whether they have N2 dz or a T4 things are not that clear:
Patients with non-small cell lung cancer who had inoperable, nonmetastatic disease gained no clinically meaningful survival advantage with immediate thoracic irradiation, even when modern megavoltage radiation therapy techniques and equipment was used in Ann Intern Med 1990 Jul 1;113(1):33-8. And in minimally symptomatic patients with locally advanced non-small cell lung cancer, “no persuasive evidence was found to indicate that giving immediate palliative thoracic radiotherapy improves symptom control, quality of life, or survival when compared with delaying until symptoms require treatment”. BMJ 2002 Aug 31;325(7362):465
What do you think?

Tuesday, July 18, 2006

Here's one from the "huh" category

In a letter I received today, summarizing a patient's recent hospitalization:

"...led us to the decision that a below-elbow amputation would help us to decrease her morbidity and would not eliminate any significant hand function."

I can't think of many things that would eliminate significant hand function MORE than a below-elbow amputation. But hey, I'm just a lung doc...

Time to Chemo and xRt

This has come up in discussions with our hem-onc dept.: Hem-onc has been frustrated by perceived delays from "first abnormal CxRay" to "definitive treatment". Our position is that diagnostic eval should be quick to try and identify possible surgical candidates and that 1-2 weeks (or even a bit more if they do get surgery) added on by staging and diagnostic procedures would not impact response to Chemo/xRt much. Other than perhaps the more aggressive small-cell case, chemo and xRt are usually either adjuvant or reverved for more advanced stages.
Do you know of actual data looking at time from diagnosis to chemo and impact on outcomes?

Obesity and lung disease

I had posted on obesity and obstructive lung disease but did not get much feedback...
JJ had an interesting aside on BMI progression over time.
Anybody (Lazar?) went to the ATS section on obesity and lung Dz? Any other insight on obstructive ventilatory defects, RAD and obesity?

Smoking cessation

JJ had posted on the JAMA article on Varenicline (Pfizer's Chantix for smoking cessation).
Has anybody had a chance to prescribe it yet?
There is a reported fairly high rate of nausea but it is also reported to be mild and transient. Any experience with that?

Monday, July 17, 2006

TBBx protocol

AK asks:

Wondering how many people out there do blind TBB's or if fluoro is pretty routine. Do people favor a particular protocol? I've seen people try to have the patient exhale, others just check if the forceps cause pain then let her rip. Would be curious to hear different techniques used out there.

Friday, July 14, 2006

56 year old woman with eosinophilia

56-year-old woman with a past medical history of asthma since age 38 with 2 previous courses of steroids, otherwise well controlled who presented with increase in non-productive cough and really very minimal SOB except on exertion. A cxr revealed b/l upper lobe infiltrates. She denies any hemoptysis and has lost about 14 pounds. She initially began her evaluation for this disease process in May 06 by ID. Her appetite is poor.


A CBC showed a white count of 17 with 42% eosinophils.
A BAL showed a cell count of 696 with 20% eosinophils, 40% macrophages, 11% lymphocytes.
A TBBX showed: Active lung injury with eosinophilia. 2. Grocott stain is negative for fungus
Based on this, the pathologist thought the ddx (which is close to mine before I saw the bx results): Diagnostic considerations include acute eosinophilic pneumonia, which is favored, an underlying infectious etiology, and Churg-Strauss syndrome/
Wegener's granulomatosis. Microbiologic and serologic studies would allow for
exclusion of the latter choices.

I would also add ABPA to that list.
Of note, the BAL was negative for all micro.

Now, my question is, would you treat this patient with steroids, since nearly everyhting on that list is trreatable with steroids, or would you proceed to open lung for a definitive dx? The reason for the latter is that even though these disease are all similarly treated, their prognosis and natural courses are different and this would be helpful for future care.
What are your thoughts?

follow-up #2 to the Woman with ground glass

Official TBBX showed:
Right lung, lower lobe, transbronchial biopsy:
1. Active interstitial inflammation with type 2-pneumocyte hyperplasia.
2. Grocott stain is negative for fungus.
3. Ziehl-Neelsen stain is negative for acid-fast bacteria.
B. Endobronchial, main carina, biopsy: Unremarkable bronchial tissue.

Don't know what this means (or doesn't mean), except that I probably could have gotton away with steroids (she's in Yemen for the next 3+ months, so I wanted to know what I was treating). If she were still here, how many would treat, how many would observe, and how many would proceed with open lung/VATs Bx?

Wednesday, July 12, 2006

Follow up to TB and ground glass

The patient from Yemen came to me on 4 drug thereapy based on a 20 mm PPD and diffuse ground glass. A repeat CT again showed the ground glass. Induced sputums were negative for AFB. I bronched her and the BAL was negative for AFB or other infection. The cell count was 540 WBC's with 13% eosinophils 27% lymphocytes, 12% neutrophils and 48% macrophages. The TBBx was showed nonspecific inflammation in the interstitium and type 2 pneumocyte hyperplasia. I changed her TB regimen to another month of rifampin only for latent TB. Because of her puritis, I went this way instead of INH.
Unfortunately, she is now on a plane to Yemen for at least the next 3 months. I would have liked to have gotton an echocardiogram and then an open lung. I was hesitant to start this woman on steroids and then send her off for 3 months, without having a definitive diagnosis.

Tuesday, July 11, 2006

Are the Eos related to the ILD?

This is a 69 y/o man sent to us for a persistent cough. He quit smoking some 34 years ago and has been fairly healthy. Dry cough is his major complaint and he does not complain of dyspnea.
No other pertinent family or social Hx.
His exam was remarkable for bibasilar "dry" crackles. No clubbing.
PFTs revealed FVC and FEV1~ 53% with a TLC~ 60% and DLCO also ~65%.
CT scan is as seen below. He had had some lab work prior to seeing us and we ordered some other tests. Of not he had a peripheral eosinophilia (11.2% - 850) and high IgE (670), ESR was 58 and ANA was negative.
A bronch revealed no eosinophils, fairly pauci-cellular BAL, negative Cxs and smears and TBBX showed some interstitial fibrosis, pneumocyte hypertrophy but was basically non-specific.
Would you regard this as "just" IPF or would you make anything out of the Eos and IgE?

Monday, July 10, 2006

Lesion and hemoptysis.

Here is a question received from the case submission form:

Patient is a 66 years old Male, Smoker since last 30 years. Hypertensive too ( IInd class)
Presently, C/O an edpisode of Haemoptysis in June 2006. Lasted for 1 and 1/2 days.

A similar episode of Haemoptysis occured in year 2002. The HRCT report at that time indicated : Small (.8cm) pre-tracheal,Right para tracheal sub-carnial lymph node. The patient was subsequently diagonsed with RENAL Stenosis and a stunt was placed without incident.


Data: Chest xray showed a small patch of moderately dense,streaky opacity at left base with localized loss of definition of cardiac apex

MRI findings : 1. Fibre lesion in right middle lobe. 2. No evidence of pleural effusion/thickening. 3.Small sub-centrimeter, pre tracheal, right para tracheal sub carnial lymphnodes. However, no evidence of significant mediastinal lymphadenopathy.

FOB + Biopsy : Bronchial mucosa shows foci of inflammatory cells in the stroma and focal area of squamous metaplasia.

Question: Is it Lung cancer : Stage 1? If not, appreciate if you can guide us further.

Friday, July 07, 2006

TB?

47 y/o female who is a resident of Yemen emigrated to USA 3 years ago presents with progressive dyspnea on exertion and also clubbing noted on physicial exam. Patient does not speak English , hence the history was obtained from her husband who has accompanied her to the clinic today. Six months ago she developed a nonproductive cough. She denies any hemoptysis. No weight loss. She states that she has been exposed to her sister-in-law who had TB. Patient denies any night sweats or weight loss. She had a PPD placed and it was 20 mm. ALso, she had a CT scan of the chest done which showed extensive abnormal areas of groundglass in a diffuse and symmetric pattern, and less prominent, septal lines most prominent at the bases.Patient denies any nausea, vomiting,diarrhea, constipation, abdominal pain, chest pain at this time.Patient denies any weight loss, fevers, or chills.
She was put on 4 drug TB regimen and then 3 sputums were induced which were all negative (and cultures all negative for 63 days). That's when I see her - 3 months after the regimen was started. To ME, she denies any dyspnea except waking up at night gasping for breath once or twice a week or two. She does have a non-productive cough. When I saw her she has itching and redness on the back of the hands. Her repeat CT again shows diffuse ground glass pattern. No opacities or lesions or infiltrates. No adenopathy. An ANA screen was was "positive", but titers not done.
So now I am stuck with someone of 4 drugs without evidence of active TB and with itching that is likely from one of the drugs. I am about to bronch her for the ground glass. Any comments/thoughts? How would you approach this case?

Wednesday, July 05, 2006

Obesity

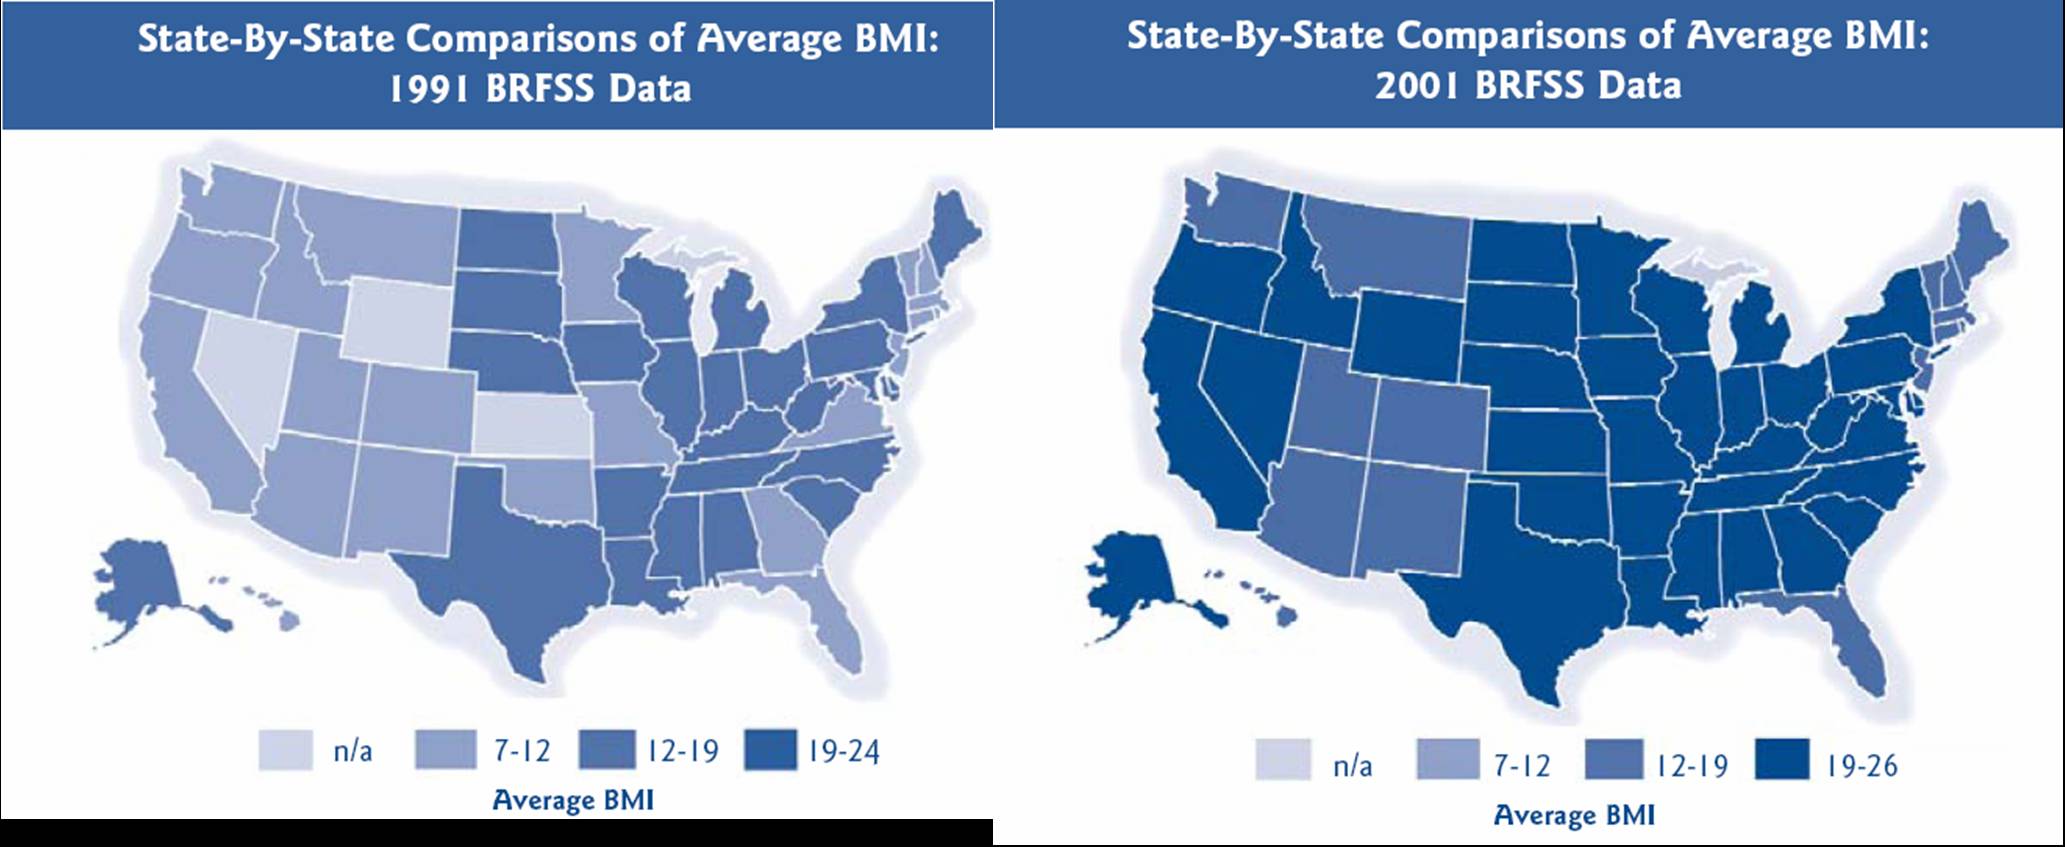
Regarding Baleeiro's post; an average BMI of 29 is pretty high, even for a midwestern state. I did find this graphic, at least showing that people are getting fatter and fatter....

As a comparison, here is the distribution of Mcdonald's in 2006....

Smoking cessation and Varenicline

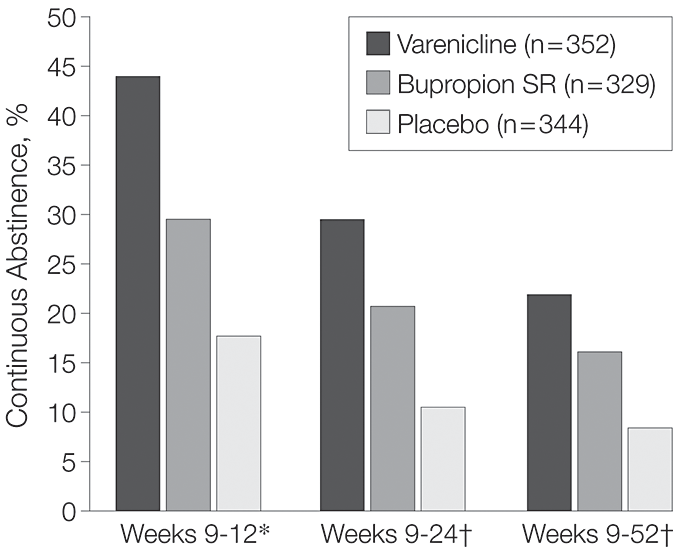
This week's JAMA (296:47-55) by Gonzales et al. has a study on smoking cessation with the new Acetylcholine receptor agonist Varenicline. It was a phase 3 randomized DB comparing 52 week abstinence between Varenicline, bupropion or placebo. Fairly compelling results with few side effects in a minority (nausea and insomnia). I wonder how expensive this stuff will be...

Obesity and obstructive lung disease

I see a lot of obese patients with mild to moderate obstruction on PFTs without smoking Hx or a clear Hx of asthma and atopy (TN has a state average BMI of 29). There was an ATS session on obesity and airways disease and a lot of interest on this correlation at NIH.
Did any of you attend the symposia on this topic? Would you manage this obstruction in a different way for this patients?

Monday, July 03, 2006

RA-associated lung disease

A 68 y/o woman with a long-standing history of Rheumatoid Arthritis and Sjogren's Syndrome (well controlled on Prednisone 7.5mg QOD, never used a steroid-sparing agent), was referred with mild but progressive dyspnea on exertion for several months.

Full pulmonary function studies show an FEV1 of 2.38, which is 102% of predicted. The FVC was 3.22 or 100% of predicted. The FEV1/FVC ratio is 74%. Total lung capacity is 101% of predicted and residual volume is 104% of predicted. The DLCO is decreased at 51%. This is unchanged from PFT's 18 months ago, with the exception of the decrease DLCO from 57%.

An HRCT (not available to upload), showed:
"Bilateral basilar predominant groundglass opacity with smooth septal
thickening. There are areas of lobular spareing.
A few well-defined scattered thin-walled cysts are present
No intrathoracic lymph node enlargement."

A subsequent bronchoscopy with BAL showed no evidence of infection. The differential had 42% lymphocytes, and 54% histiocytes. Transbronchial biopsies were read as: "Chronic and granulomatous inflammation. Amorphous acellular material. Congo red stain negative for amyloid. GMS stain for fungal organisms negative."

Question: How should one approach this case? Would you take the CT scan, the lack of infection on BAL, and the lymphocytosis on BAL and treat with a presumptive diagnosis of RA-associated NSIP by increasing the steroid dose? Or would you proceed with a surgical lung biopsy. Any other thoughts?

Sunday, July 02, 2006

Follow-up to AFB

This was the 83 y/o man with no COPD, no TOB Hx with a respiratory tract infection with AFB growth from the sputum.
I ended up doing a combination of the suggestions from JJ and Jeff H: I hoped and assumed the AFB was not TB but with the positive PPD, and since I should not start just INH, I did initiate therpay with 4 drugs for TB.
The Cxs came back with a pan-sensitive MTb, ETH was discontinued and he is doing very well on RIF/PZA/INH.
Are you surprised at the paucity of symptoms and fairly benign CxR? I know Tb can present in many unusual ways but I like to see at least something abnormal with TB...